What the anion gap estimates
The anion gap is a calculated value that serves to estimate the balance between measured electrolytes in the blood and the unmeasured ions that are not directly shown on a serum chemistry panel. It is often used as a diagnostic marker for acid-associated problems and other metabolic imbalance patterns. In simple terms, it helps clinicians look for clues about whether the body’s electroneutrality is being maintained as expected.
Blood contains positively charged particles, called cations, and negatively charged particles, called anions. The major measured cations and anions on routine serum electrolytes testing include sodium, chloride, and bicarbonate. Because the body must stay electrically balanced, any difference between the main measured ions can suggest the presence of unmeasured anions or other shifts in plasma chemistry. That difference is what the anion gap estimates.
The clinical significance of the anion gap is not that it diagnoses a single disease. Instead, it provides a framework for interpretation of lab results in the setting of illness, especially when evaluating acid-base disorder patterns. A high or low result may point to a broad range of causes, so the number must always be considered in diagnostic context with the patient’s symptoms and other blood chemistry findings.
Why sodium is included in the formula
Sodium is included in the anion gap formula because it is the primary measured cation in the extracellular compartment and a key contributor to plasma charge balance. In standard lab practice, the usual formula is:
anion gap = sodium - (chloride + bicarbonate)Some versions of the formula may incorporate potassium, but sodium is the main analyte because it accounts most of the measured positive charge. The formula matches the main cation, sodium, against the main measured anions, chloride and bicarbonate. The difference provides an estimate of the amount of unmeasured negatively charged substances in the blood.
This is where the concept of electroneutrality becomes important. The body’s fluids must remain electrically balanced, so the total positive and negative charges should generally match. Since not all ions are directly measured, the anion gap uses sodium as the anchor for the calculation. Without sodium, there would be no straightforward way to estimate the gap between measured cations and measured anions.
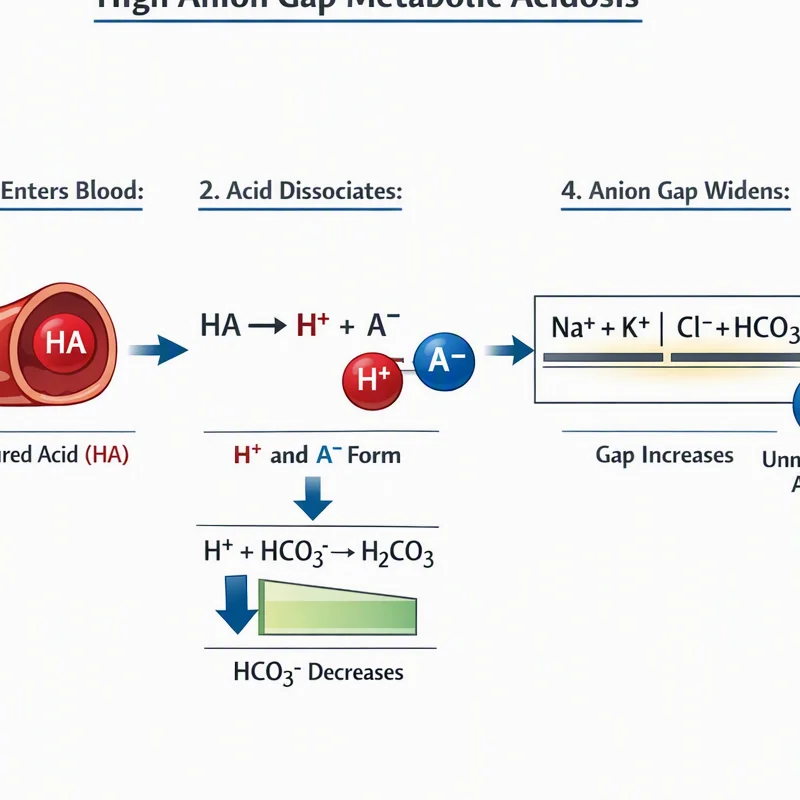
The role of bicarbonate is also critical. When bicarbonate decreases, as it often does in metabolic acidosis, the calculated gap may rise if the lost bicarbonate is replaced by unmeasured acids. This makes the formula valuable for identifying certain metabolic disturbance patterns that are not obvious from sodium alone.
How an Anion Gap Calculator uses sodium values
An Anion Gap Calculator is a useful tool that uses the formula automatically from your serum sodium, serum chloride, and serum bicarbonate values. The calculator does the calculation efficiently and reduces the chance of arithmetic mistakes during lab interpretation. It is especially helpful when reviewing multiple lab values in a short time or when comparing repeated results over time.
The calculator’s output represents a gap calculation based on standard serum chemistry data. Because sodium is the main starting point, even small changes in serum sodium can influence the final number. However, the effect is best understood in combination with chloride and bicarbonate rather than sodium by itself. A change in one analyte may shift the result while the underlying physiology remains steady or changes in the opposite direction.
For example, if sodium remains unchanged but bicarbonate falls, the calculated gap may rise. If sodium falls or rises substantially, the absolute gap may also shift, but interpretation depends on whether the change reflects an actual acid-base disturbance, dilution, water balance changes, or another clinical factor. That is why an Anion Gap Calculator is an approximation tool, not a standalone diagnosis.
In practice, the calculator helps arrange lab results into a pattern that supports clinical reasoning. It can identify a possible abnormal result, but the next step is always to interpret the number in relation to the overall electrolyte panel, symptoms, and other findings.
How increased sodium vs reduced sodium can suggest about the calculated gap
Variations in sodium levels may alter the anion gap in a manner that are clinically meaningful but not always straightforward. In hypernatremia, sodium is increased, which can shift the calculated value upward. In hyponatremia, sodium is reduced, which can reduce the result. Still, the relationship is not purely mathematical; it is also tied to water balance, plasma concentration, and the broader state of acid-base balance.
Elevated sodium does not automatically mean a high anion gap disorder is present. A patient can have hypernatremia from fluid loss or water loss without a primary acid-base problem. Likewise, low sodium may indicate water excess relative to solute, endocrine issues, kidney-related problems, or other causes that do not directly produce a high anion gap or low anion gap. The key is to avoid treating the anion gap as a sodium-only metric.
Serum osmolality can be useful to put sodium changes into better context. Because sodium strongly influences osmolality, marked shifts in sodium may indicate a broader disturbance in fluid distribution. That disturbance may coexist with an acid-base issue, but it does not establish one. The best interpretation combines sodium with chloride, bicarbonate, and the patient’s overall status.
When sodium is abnormal, it can also affect the perceived severity of an acid-base disorder. A calculated gap may appear greater or reduced than expected because the baseline concentration of the dominant cation has changed. For that reason, a careful reviewer should ask whether the sodium abnormality is shaping the result, hiding another issue, or simply occurring alongside it.
Typical causes of a high anion gap
A elevated anion gap typically indicates that unmeasured acids are present in greater amounts. This finding is often observed in acid buildup, where bicarbonate is consumed as it counteracts acid. As bicarbonate decreases, the calculation leaves a bigger gap between sodium and the measured anions.
One common cause is excess lactate, which occurs when lactate builds up faster than the body can clear it. Lactate is an unmeasured anion in standard routine labs, so it can raise the gap. This may happen in shock, poor tissue oxygen delivery, severe illness, or other conditions that change metabolism and perfusion.
Another key cause is ketone buildup. In this condition, ketone bodies rise and contribute unmeasured anions. It is often associated with diabetes, prolonged fasting, or alcohol-related metabolic changes. The accumulation in unmeasured acids shifts the blood chemistry pattern and can produce a markedly high gap.
Kidney-related toxin accumulation from impaired kidney clearance is also a classic contributor. When renal function declines significantly, acids and other solutes that should be excreted can collect. This affects the blood’s balance of measured and unmeasured components, making the anion gap a useful clue in the broader assessment of kidney-related metabolic disturbance.
Additional causes can include toxins, severe illness, and mixed disorders. Still, the core anion gap calculator with albumin idea remains the same: a high gap usually means the body has built up acids or kept unmeasured anions that are not reflected directly in the routine electrolyte values.
When a standard anion gap can still be misleading
A normal result does not always mean the electrolyte picture is truly unchanged. A number of factors can make the anion gap look acceptable even when a serious problem is present. One major factor is albumin, the main negatively charged protein in plasma. Because albumin contributes substantially to the usual gap, low albumin can hide an elevated gap state.
This is why clinicians sometimes use a corrected anion gap. The correction adjusts for hypoalbuminemia so the result better reflects the real burden of unmeasured anions. Without this step, a patient with low albumin may appear have a normal gap even though a meaningful acid-base disorder is present underneath.
Lab error is another problem. Sample handling problems, measurement variability, or reporting mistakes can alter sodium, chloride, or bicarbonate values enough to shift the result. A suspicious number should always be rechecked against the full lab record and the clinical picture.
The chloride shift can also complicate interpretation. If chloride rises to counterbalance another change, the calculated gap may stay within the expected reference range even when a significant process is occurring. In other words, the body may maintain apparent balance on paper while still undergoing a real metabolic change.
For these reasons, a normal gap should be viewed as one clue, not the final answer. It can be especially misleading in mixed disorders, low albumin states, or cases where fluid shifts alter measured electrolyte concentrations.
How to understand outcomes in contextual terms
The best clinical interpretation of an anion gap result comes from combining it with the remainder of the patient’s data. Sodium, chloride, and bicarbonate show only a portion of the story. Additional information such as potassium, renal function, symptoms, medications, and the presence of illness all influence the meaning of the number.
An arterial blood gas is especially helpful when an acid-base problem is suspected. It offers information about pH, carbon dioxide, and compensatory changes that can show whether the patient has metabolic acidosis, respiratory issues, or a mixed disorder. In many cases, the anion gap is only one piece of the larger acid-base puzzle.
It is also important to assess whether compensatory changes make physiologic sense. The body often responds to a metabolic disturbance with predictable respiratory or renal adjustments, but these responses may be incomplete or masked by another condition. That is why the calculated gap should be interpreted alongside symptoms, examination findings, and the overall serum electrolytes pattern.
In everyday practice, the best approach is to think in stages:
- Verify whether sodium, chloride, and bicarbonate are abnormal. Decide whether the calculated gap is high, normal, or low. Consider albumin and consider a corrected anion gap when needed. Look for renal impairment, lactic acidosis, ketoacidosis, or uremia. Verify the result with broader clinical context and, when appropriate, arterial blood gas testing.
This stepwise approach strengthens lab interpretation and reduces the risk of overreading a single abnormal result. An abnormal result can be highly informative, but only when viewed as part of a complete diagnostic context.
Frequently asked questions about sodium and the anion gap
What’s the role of sodium in the anion gap?
Sodium is the main measured cation used in the anion gap formula. It gives the starting point for the calculation, which matches sodium against chloride and bicarbonate to estimate the level of undetected anions in plasma. If there were no sodium, the calculation would not work as a reliable assessment tool for electrolyte stability and acid-base issues.
Why does the anion gap formula include sodium?
The formula contains sodium because it is the dominant positively charged analyte in routine serum electrolytes screening. Since the body must maintain electroneutrality, sodium is used as the reference point for assessing measured cations with measured anions. This can help reveal hidden alterations in blood chemistry that may point to metabolic disturbance.
Can low sodium affect the anion gap result?
Yes. Hyponatremia can decrease the calculated result because sodium is the key initial value in the formula. But the implication of that change depends on the full clinical picture, including chloride, bicarbonate, serum osmolality, and whether there is a true acid-base disorder. Low sodium alone does not establish the cause.
Does a normal anion gap eliminate acid-base problems?
No. A regular result cannot eliminate all acid-base disturbances. Problems can be obscured by low albumin, testing error, a chloride shift, or mixed disorders. For this reason a normal value should be interpreted with the rest of the electrolyte panel, the patient’s symptoms, and any arterial blood gas results when available.
How exactly does an Anion Gap Calculator help interpret lab results?
An Anion Gap Calculator rapidly performs the gap calculation using serum sodium, chloride, and bicarbonate. It assists interpret lab values, identify a possible elevated anion gap or decreased anion gap, and support faster lab interpretation. However, it does not replace clinical interpretation, since albumin, renal function, and the broader diagnostic context still count.