How the Anion Gap Is Measured
An anion gap is a computed result that helps healthcare providers assess the relationship between primary electrolytes in the blood. It is based mainly on sodium, chloride, and bicarbonate, which are routinely reported on regular chemistry panels. Even though the number itself is calculated, it can indicate important clues about an acid-base disorder or a wider metabolic disorder.
The core concept is straightforward: blood contains positively charged particles and negative ions, and these should be maintained in a fairly consistent balance. The anion gap calculator estimates the gap between measured cations and measured anions. A change in that difference can suggest the presence of unmeasured anions in the bloodstream.
Clinicians use this result as part of clinical assessment and lab interpretation, especially when they need to determine whether a patient’s acid-base balance is shifting in a harmful direction. The anion gap is not a standalone diagnosis, but it is a helpful diagnostic tool that helps interpret other serum electrolytes and blood chemistry results.
How an Anion Gap Calculator Is Used
An anion gap calculator is applied to rapidly calculate anion gap from values already reported in a serum chemistry panel or a basic metabolic panel. These lab panels are common forms of blood test reporting, and they offer a practical snapshot of key blood chemistry markers. The calculator takes the reported numbers and returns an anion gap result that can be assessed during medical interpretation.
In practice, the calculator is often applied during a physician evaluation when a patient has unexplained symptoms, abnormal labs, or concern for an acid-base problem. It helps organize the next steps in a metabolic acidosis workup by showing whether the issue may involve excess acids, a loss of bicarbonate, or another shift in serum electrolytes.
Some calculators also help users interpret normal values by comparing the result with a reference range. This can be helpful for anyone trying to make sense of a lab panel, although final test interpretation should always be done in context. The number is most relevant when combined with symptoms, other lab data, and the overall clinical picture.
Why Healthcare providers Order an Anion Gap Test
Healthcare providers request an anion gap test to evaluate metabolic acidosis and various forms of acid-base balance disturbance. A rising or lowering anion gap can indicate an underlying condition that is not obvious from symptoms alone. Because the result reflects how measured ions relate to each other, it can help spot an electrolyte imbalance that may otherwise be missed.
This is especially important when a person appears ill, has altered breathing patterns, or has lab findings that indicate a broader metabolic issue. The anion gap is often one piece of a larger workup that may include repeat blood testing, kidney markers, glucose levels, and a blood gas. Together, these findings support more accurate diagnosis and treatment planning.
Another reason the test is ordered is to help assess kidney function. The kidneys help regulate acid and electrolyte levels, so reduced function can change the balance of acids and bases in the blood. When kidney performance declines, the anion gap may go up as acids accumulate or may help confirm that something more than simple dehydration is happening.
How High and Reduced Anion Gap Results Can Indicate
A high anion gap usually means there are additional acids in the blood or that not directly measured substances are affecting the calculation. This is commonly a sign of a significant acid-base problem and can help clinicians identify conditions such as lactic acidosis, diabetic ketoacidosis, or additional illnesses that produce acid rapidly. A high result does not name the cause by itself, but it can narrow the differential diagnosis.
A low anion gap is not as common, but it can be just as significant to notice. It may occur when albumin is low, when lab values are affected by technical or measurement issues, or when other substances are influencing the balance of charges in the blood. In some cases, a low result is a clue to a hidden condition; in other cases, it is a temporary finding that should be rechecked.
Both results require careful context. A single number should not be treated as a diagnosis. Instead, it is one data point used in lab interpretation, especially when the clinician is trying to understand an unexplained anion gap result in relation to symptoms, other chemistry values, and the patient’s overall condition.
Common Causes of an Abnormal Anion Gap
A common reason of an elevated anion gap is diabetic ketoacidosis, a serious complication of diabetes in which acidic ketones accumulate in the blood. A further cause is exposure to toxins, which can bring in or trigger acids that change the expected electrolyte relationship. These causes are especially important because they may require urgent evaluation and treatment.
Lactic acidosis is another major cause of an abnormal result. It can develop when tissues do not get enough oxygen or when severe illness alters how the body produces and clears lactate. This condition is often seen with infection, shock, or other critical illnesses, and it is a key reason clinicians monitor the anion gap in acute care.
Albumin also is important because it is a major negatively charged protein in the blood. When albumin is low, the anion gap may look reduced than expected even if an acid-base problem is present. In addition, kidney disease and renal failure can cause abnormal retention of acids, shifting the result upward. Because of that, clinicians interpret anion gap frequently interpret the anion gap alongside kidney labs and the patient’s history.
How to Understand the Finding with Other Labs
Understanding the finding correctly relies on the anion gap formula, which uses sodium, chloride, and bicarbonate to estimate the gap between measured cations and anions. But the formula alone is not enough. Clinicians often order a blood gas to see whether the patient is acidotic or alkalotic and to understand how well breathing and metabolism are compensating.
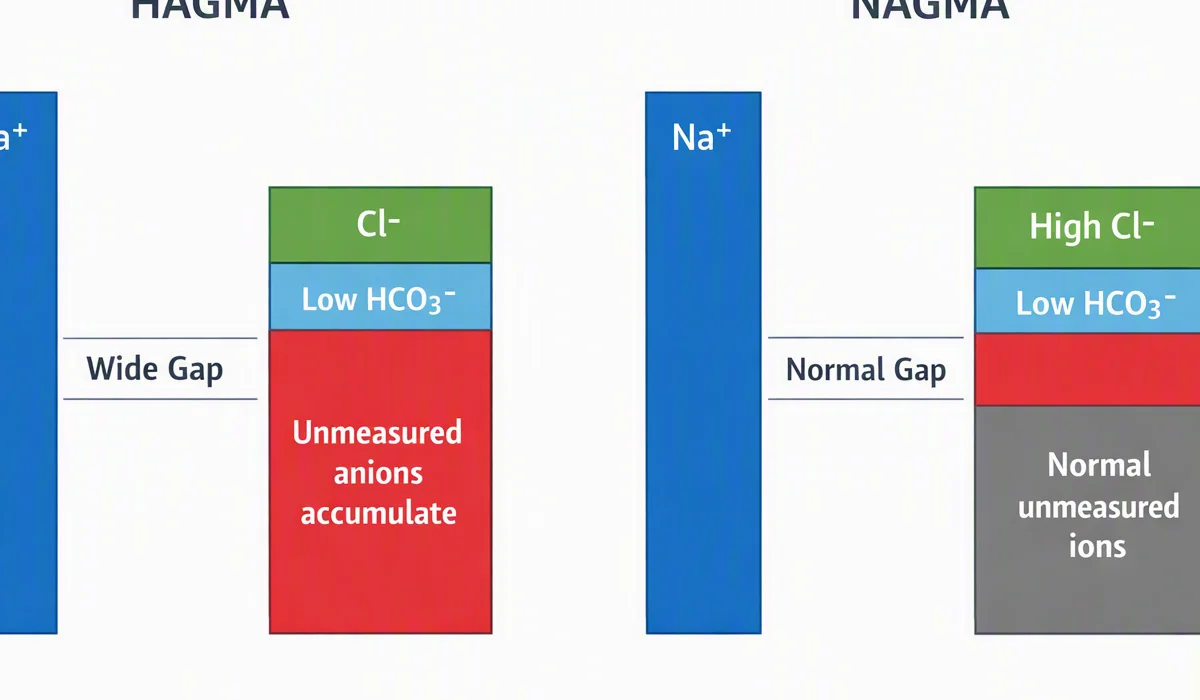
Potassium may also be assessed, even though it is not always part of the standard formula. It can help define the broader electrolyte pattern and may influence the full clinical picture. In some situations, the lab panel includes enough information to point to an answer quickly; in others, the pattern is subtle and requires more evaluation.
Albumin correction is especially relevant when albumin is abnormal. A corrected anion gap can provide a more accurate estimate of whether the true gap is elevated. This matters because low albumin can mask an otherwise meaningful abnormality. By applying albumin correction, clinicians improve the quality of medical interpretation and reduce the chance of missing a serious disorder.
In short, the anion gap should be read as part of a full lab panel, not as a stand-alone finding. The best interpretation comes from combining the result with symptoms, history, and other data from the serum chemistry panel or basic metabolic panel.
Whenever an Anion Gap Result Needs Medical Review
An abnormal anion gap calls for clinical attention when it appears with concerning symptoms or when the overall clinical picture suggests a serious metabolic problem. Symptoms such as mental confusion, fast breathing, extreme weakness, vomiting, or severe illness can indicate that the body is struggling to maintain normal acid-base balance. In these cases, the lab result may be an first alert rather than a simple abnormality on paper.
Emergency care may be needed if the abnormal result is paired with signs of shock, severe dehydration, altered mental status, or suspected poisoning. Conditions like sepsis can also drive significant changes in the anion gap, especially when lactic acidosis develops. In such instances, the number helps support rapid diagnosis and treatment, but it should never delay urgent clinical action.
Dehydration can also affect the lab picture, sometimes making abnormalities look more pronounced. Even if a result turns out to be short-lived, it is worth reviewing when the patient has symptoms or abnormal findings that do not fit a simple explanation. A clinician may repeat testing, order a blood gas, or evaluate for kidney involvement and other causes of acid-base disturbance.
FAQs On Anion Gap Calculators
What can an anion gap calculator tell you
An anion gap calculator gives you the computed difference between main measured electrolytes in the blood, primarily sodium, chloride, and bicarbonate. It may reveal whether there may be extra acids or other unmeasured substances affecting the blood’s acid-base balance. Clinicians use it clinically as a diagnostic tool to support lab interpretation and guide next steps.
What’s a normal anion gap range?
The normal range can vary slightly depending on the lab and the formula used, so the reference range on the report matters. Because of that variation, it is best to use the specific range shown with the lab values rather than assuming one universal number. The most important question is whether the result is within that lab’s normal values.
Does a high anion gap always mean a serious problem?
Not always, but it can signal a significant issue that deserves prompt evaluation. A high anion gap is often seen with metabolic acidosis, lactic acidosis, diabetic ketoacidosis, kidney disease, or toxins. The seriousness depends on the full clinical context, including symptoms, the blood gas, and other abnormal labs.
Can a low anion gap be harmless?
Yes, sometimes a low anion gap is temporary or related to a non-dangerous lab variation. However, it can also occur when albumin is low or when another condition is affecting the calculation. If the result is unexpectedly low, clinicians may repeat the test and review the full lab panel to make sure nothing important is being missed.
Why is albumin important when interpreting the anion gap?
Albumin is important because it carries a negative charge and has a major effect on the anion gap result. When albumin is low, the gap may appear lower than it really is, which is why albumin correction can be useful. A corrected anion gap gives a more accurate view of whether there is a true acid-base disorder or an unmeasured anion problem.