The gap between ions is a helpful way to look at the balance of minerals in the blood and to support recognition of certain types of pH-related problems. In chronic kidney disease, it can provide important clues about acid buildup, acid-base status, and how effectively the kidneys are handling acid and waste products. A quick lab test or an Anion Gap Calculator can help clinicians judge whether the pattern of blood chemistry suggests a buildup of undetected anions, a different cause of acidosis, or a result that needs further medical interpretation.
Although the concept can sound specialized, the basic idea is easy to grasp: the body’s major charged particles should stay in harmony. When that balance shifts, the anion check here gap can go up, decrease, or stay normal depending on the cause. In chronic kidney disease, those changes may suggest renal dysfunction, retention of acids, or other processes affecting lab values.
What the Anion Gap Measures
The anion gap is a derived value that helps estimate the difference between the main positively charged and negatively charged substances in the blood. It is commonly derived from an electrolyte panel or more comprehensive blood chemistry testing. The most common ingredients are sodium, chloride, and bicarbonate, with potassium sometimes included depending on the formula used.
In practical terms, the anion gap helps gauge the amount of unmeasured anions in the bloodstream. These are negatively charged substances that are not directly reported on a standard lab test but still influence acid-base status. Examples include proteins, phosphates, sulfates, and certain acids that can build up during illness. Because the calculation is indirect, it is best understood as a diagnostic marker rather than a diagnosis by itself.
The classic anion gap calculation is:
Anion gap = Sodium − (Chloride + Bicarbonate)
Some versions also include potassium, which slightly changes the result. That is one reason an Anion Gap Calculator can be helpful: it follows the chosen formula consistently and reduces arithmetic errors when reviewing lab values.
For most people, the anion gap is a look at the body’s electrolyte imbalance and overall acid-base balance. When the gap increases, it often suggests that extra acids or acid-related substances are present. When it decreases, the issue may involve low proteins, measurement differences, or less commonly unusual blood chemistry patterns.
Why the Anion Gap May Vary in Chronic Kidney Disease
Chronic kidney disease impairs how the kidneys filter waste and control acids. As kidney function decreases, the body may have trouble eliminating acid and maintaining normal acid-base balance. This can cause metabolic acidosis, especially when the kidneys can no longer remove enough acid or produce enough bicarbonate to keep up with daily acid production.
One important concept is acid retention. Healthy kidneys eliminate acid byproducts of metabolism. With renal impairment, those byproducts can accumulate. Over time, this boosts the likelihood of a higher anion gap because more unmeasured anions are present in the blood.
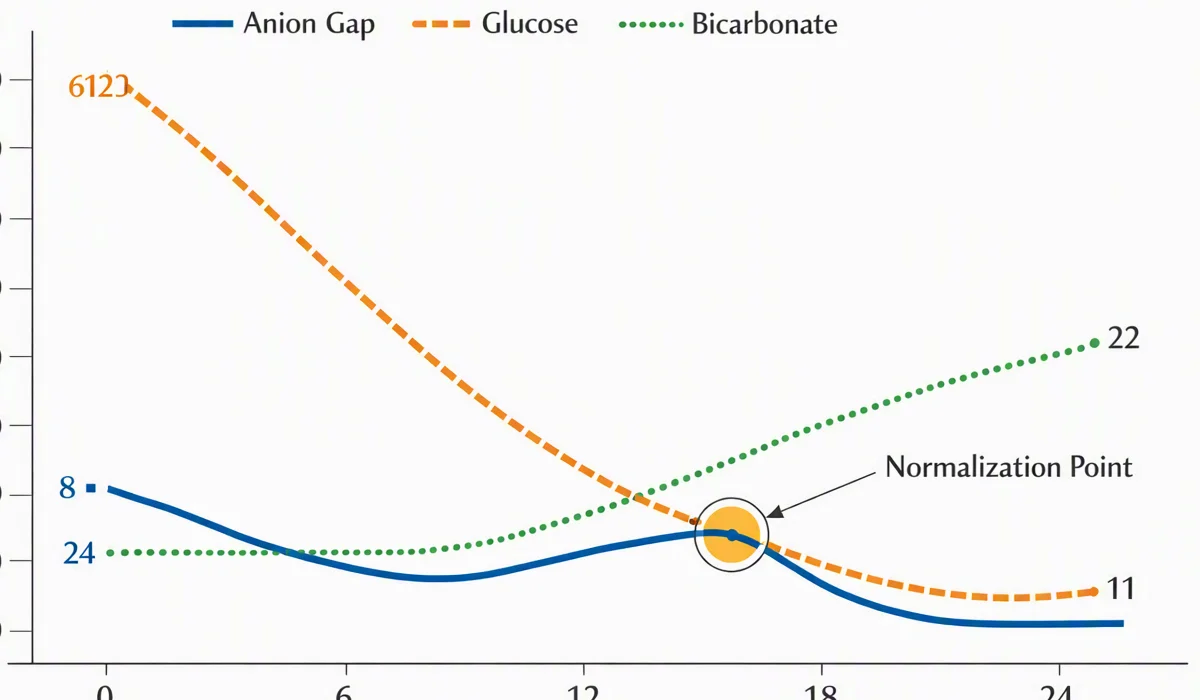
That said, chronic kidney disease does not always produce the same acid pattern. Some people develop high anion gap metabolic acidosis, while others have normal anion gap metabolic acidosis. The difference varies with how advanced the kidney disease is, how much acid has accumulated, whether bicarbonate is being lost through other pathways, and whether another problem is contributing to the disturbance.
In earlier stages of CKD, a normal anion gap pattern may appear if the body is losing bicarbonate without yet accumulating large amounts of unmeasured acids. In more advanced disease, uremia and retained metabolic waste can drive the anion gap upward. This is why clinicians look at the full set of blood test results rather than relying on one number alone.
Standard, Decreased, and High Anion Gap Values
The expected range for the anion gap can differ by laboratory because various analyzers and formulas are used. In many settings, the usual range is roughly within the lower teens, but the exact cutoff should always be interpreted using the lab’s own benchmark. A result outside the expected range does not automatically mean disease; it means the value needs clinical context.
A increased anion gap usually means that additional acids or acid-related substances are present in the blood. Common causes include metabolic acidosis from renal failure, lactic acid buildup, ketoacidosis, or toxin exposure. In CKD, a rising gap often reflects accumulated acidic waste and lessened ability to clear it.
A decreased anion gap is less common. It may be seen with low albumin levels, lab variation, or certain unusual conditions affecting blood proteins or measurement. Because albumin carries negative charge, low albumin can reduce the apparent gap even when acid-base issues are present. This is why hypoalbuminemia matters so much in interpretation.
It helps to think of the anion gap as a clue, not a verdict. A value that looks normal may still hide an acid-base problem if albumin is low. A value that looks high may reflect true accumulation of acid, but the cause still needs to be determined. That is where careful clinical interpretation becomes essential.
How an Anion Gap Calculator Is Used
An Anion Gap Calculator is a handy utility for rapidly performing the anion gap calculation from available lab values. It generally uses sodium, chloride, and bicarbonate, and some versions also allow potassium to be included. The calculator can be very helpful when reviewing an electrolyte panel or interpreting detailed serum chemistry results.
Using the calculator is straightforward:
- Type in the measured sodium value. Type in the chloride value. Type in the bicarbonate value. Enter potassium if the formula being used uses it. Review the result against the lab’s reference range.
In real clinical work, the calculator is not used in isolation. It is part of a broader review of the acid-base disorder, the patient’s symptoms, and other markers of kidney and metabolic health. For example, a low bicarbonate level with a high anion gap might suggest one type of metabolic acidosis, while low bicarbonate with a normal gap may point to a different process.
The calculator also supports uniformity. Different formulas and slight measurement differences can affect the result, so a tool that clearly shows the inputs can improve the reliability of the initial screen. Still, the number itself is only the start of interpretation. The surrounding context, including kidney dysfunction and overall blood chemistry, determines what the result means.
Frequent Causes of Increased Anion Gap in CKD
With CKD, an elevated anion gap often points to uremia, the buildup of waste products that healthy kidneys would normally eliminate. These leftover compounds add to the pool of unmeasured anions, leading to high anion gap metabolic acidosis. As renal failure progresses, acid handling becomes less efficient, and the blood may become increasingly acidic.
However, CKD is not the only likely explanation. Other causes can coexist with kidney disease and intensify the result. Typical examples include:
- Lactic acidosis, which can occur when tissues are under stress or not getting enough oxygen. Ketones, which rise in states such as diabetic ketoacidosis or prolonged fasting. Toxins, including certain ingestions that alter blood chemistry and increase acid load.
These factors are important because they can coexist with CKD. A person with chronic kidney disease may have a high anion gap due to reduced clearance of acids, but another trigger can increase it more. That is why the pattern is considered a diagnostic marker rather than a complete answer. Clinicians use the result to direct the next step in evaluation, not to stop at the number alone.
The underlying theme is metabolic acid load. When the body produces more acid than it can remove, or when the kidneys cannot clear what is produced, the balance moves. The anion gap helps identify that shift early enough to support treatment planning and monitoring.
Correcting the Anion Gap for Albumin
One of the most important improvements in interpretation is adjusting for albumin. Because serum albumin is a major negatively charged protein in the blood, low albumin can make the anion gap look lower than it truly is. This is especially important in sick patients and in people with hypoalbuminemia.
When albumin is low, the measured anion gap may underestimate the amount of acid present. A corrected anion gap adjusts for that effect so the clinician can better estimate the true acid burden. Without this adjustment, a person with CKD and low albumin might appear to have a normal gap even though significant metabolic acidosis is present.
The exact correction formula may vary, but the principle is the same: lower albumin reduces the apparent gap, so the observed number should be adjusted upward when albumin is below normal. That is why a good Anion Gap Calculator may include an option for albumin adjustment or, at minimum, remind users to consider it separately.
Albumin correction is especially useful when evaluating acid-base patterns in chronic illness, because hypoalbuminemia can coexist with renal impairment, malnutrition, inflammation, or other conditions that influence blood chemistry. Correcting the value can change how the clinician views the severity and type of acid-base disturbance.
How Clinicians Interpret the Result
Clinicians review the anion gap as part of a full acid-base workup. Clinicians look at the computed number, the bicarbonate value, the chloride value, the patient’s overall condition, and whether there is evidence of electrolyte imbalance or other metabolic disorders. The purpose is to determine whether the pattern fits an acid-base disorder and what is causing it.
Within chronic kidney disease, a higher gap can suggest the presence of acid buildup and advancing declining kidney function. A normal gap does not rule out medically significant acidotic states, particularly when bicarbonate is low. This may instead indicate normal anion gap metabolic acidosis, which can develop when bicarbonate is lost or supplanted by chloride in a way that keeps unchanged the measured gap.
That distinction is important because it alters the likely causes and the diagnostic path. For instance, a elevated gap may cause clinicians to consider uremia, lactic acidosis, ketones, or toxins. A typical gap pattern may cause them to focus more on bicarbonate loss, medication effects, or tubular handling of acid and chloride. Either way, the result guides diagnosis and treatment planning.
Evaluation also includes compensatory responses into account. The body may modify breathing and fluid handling in response against acid-base changes. These compensatory mechanisms can alter symptoms and lab patterns, so the anion gap value should be considered alongside the rest of the clinical picture rather than as a stand-alone answer.
When to Seek Medical Evaluation
People with chronic kidney disease should obtain medical evaluation if they notice symptoms that could suggest more severe acidosis or a significant electrolyte problem. Warning signs may include shortness of breath, pronounced fatigue, confusion, an upset stomach, weakness, or a general sense that something is off. These symptoms are not specific to the anion gap, but they can point to a need for prompt review of blood test results.
If a recently obtained lab report shows an elevated anion gap, especially along with decreased bicarbonate or indications of worsening kidney status, it should be discussed with a clinician. The same is true if there is known renal impairment and symptoms are changing. In some cases, the issue may be mild and monitored over time. In others, it may point to a more serious acid-base disorder that needs management.
Do not rely on a calculator alone if symptoms are present. The lab test result is one piece of the picture, and clinical assessment is needed to relate the value to the person’s condition. The most important step is understanding whether the result represents a stable chronic pattern or a recent and potentially concerning shift in acid-base balance.
FAQ
What is the anion gap in chronic kidney disease?
The anion gap in chronic kidney disease is a computed blood value used to evaluate acid-base balance. It can show whether there is a buildup of unmeasured anions related to acid retention, metabolic acidosis, or other factors. In CKD, it is often used as a guide to help interpret kidney-related blood chemistry changes.
Why does chronic kidney disease cause a high anion gap?
Chronic kidney disease can cause a high anion gap because reduced kidney function leads to retention of acids and other waste substances. This buildup, often called uremia, increases the number of unmeasured acids in the blood and can result in high anion gap metabolic acidosis. Other problems such as lactic acidosis, ketones, or toxins can also play a role.
Can the anion gap be normal in chronic kidney disease?
Yes. The anion gap can be normal in chronic kidney disease, especially when the acid-base pattern is normal anion gap metabolic acidosis or when albumin is low and the result has not been corrected. A normal value does not exclude acidosis, so the full set of lab values and the patient’s overall condition need to be taken into account.
How do you determine the anion gap from lab values?
The standard calculation is sodium minus the total of chloride and bicarbonate: anion gap = sodium − (chloride + bicarbonate). Certain equations also include potassium. An Anion Gap Calculator can calculate it automatically from the available electrolytes and help avoid errors when reviewing the electrolyte panel.
Why is albumin correction important when interpreting the anion gap?
Albumin correction is important because serum albumin is negatively charged, and low albumin can make the anion gap appear falsely low. In people with hypoalbuminemia, the measured value may miss an underlying acid problem unless a corrected anion gap is used. This adjustment improves clinical interpretation and helps show the true acid burden.