An anion gap calculator is a useful tool for interpreting acid-base balance and improving the differential diagnosis of metabolic acidosis. It assists clinicians and learners turn a basic set of electrolytes into a clearer diagnostic approach by showing whether unmeasured acids may be present. When used properly, the anion gap is more than a number; it is a roadmap to next steps in metabolic acidosis evaluation, especially when paired with blood gas analysis and the rest of the electrolyte panel.
The value is derived from routine serum chemistry results, most often sodium, chloride, and bicarbonate, with potassium sometimes included. Because the result reflects the balance between measured cations and anions, it provides a rapid window into possible electrolyte abnormalities, unmeasured anions, and acid retention. The key is not just calculating it, but using it in clinical context.
What is the anion gap?
The anion gap is a derived measurement that estimates the difference between measured positive and negative ions in the blood. In plain language, it shows the gap between the major measured cation, sodium, and the major measured anions, especially chloride and bicarbonate. This difference exists because the body contains many unmeasured anions and cations that are not directly listed in routine lab results.
In acid-base physiology, the buffer system helps maintain pH within a narrow range. When acids build up, their anions may not be immediately captured on standard labs. The anion gap gives indirect evidence of that accumulation. For this reason, the anion gap is key to interpreting acid-base disorders, particularly metabolic acidosis.
Most anion gap calculation methods rely on a basic formula based on measured electrolytes. The result is not a diagnosis by itself, but it can signal when additional evaluation is needed. That is why an anion gap calculator is helpful in everyday practice: it turns raw lab values into a decision point.
How does the anion gap aid identify acid-base disorders?
The anion gap assists differentiate between major forms of metabolic acidosis. A high anion gap implies that acids are accumulating in the body, frequently from lactate elevation, ketone production, toxin exposure, or slower removal. A normal anion gap indicates a different pattern, often one in which bicarbonate is being lost and replaced by chloride, producing hyperchloremic acidosis.
This distinction matters because acid-base disorders are not all managed the same way. A high gap points you toward causes such as lactic acidosis, ketoacidosis, or renal impairment. A normal gap often suggests gastrointestinal losses or tubular defects. The value therefore acts as a branching point in the diagnostic workflow.
In practice, a clinician reviews the anion gap alongside the blood gas, pH, and bicarbonate level. If bicarbonate is low and the anion gap is high, the pattern supports high anion gap metabolic acidosis. If bicarbonate is low but the anion gap is normal, the pattern is consistent with normal anion gap metabolic acidosis. That first branch determines what to test next.
How do you calculate the anion gap?
The usual anion gap formula is:
Anion gap = sodium - (chloride + bicarbonate)
Some clinicians add potassium, but many do not because it has a small effect in most settings. A common alternative is:
Anion gap = (sodium + potassium) - (chloride + bicarbonate)
The calculator usually draws from values on a basic metabolic panel, which is part of a routine electrolyte panel. Since the result varies with the exact numbers entered, even small shifts in sodium, chloride, or bicarbonate can affect the interpretation.
For example, if sodium is 140, chloride is 102, and bicarbonate is 24, the anion gap is 14. That may fall within or slightly above the local reference interval, depending on the laboratory. The point is that the number must be interpreted against the lab’s method and context, not as a universal fixed value.
What is a normal anion gap range?
The normal range is most accurately interpreted as a reference range, instead of an absolute standard. Various labs use different instruments and methods, so the expected value can vary because of lab variation. In addition, the measured range may differ depending on whether potassium is included in the calculation.
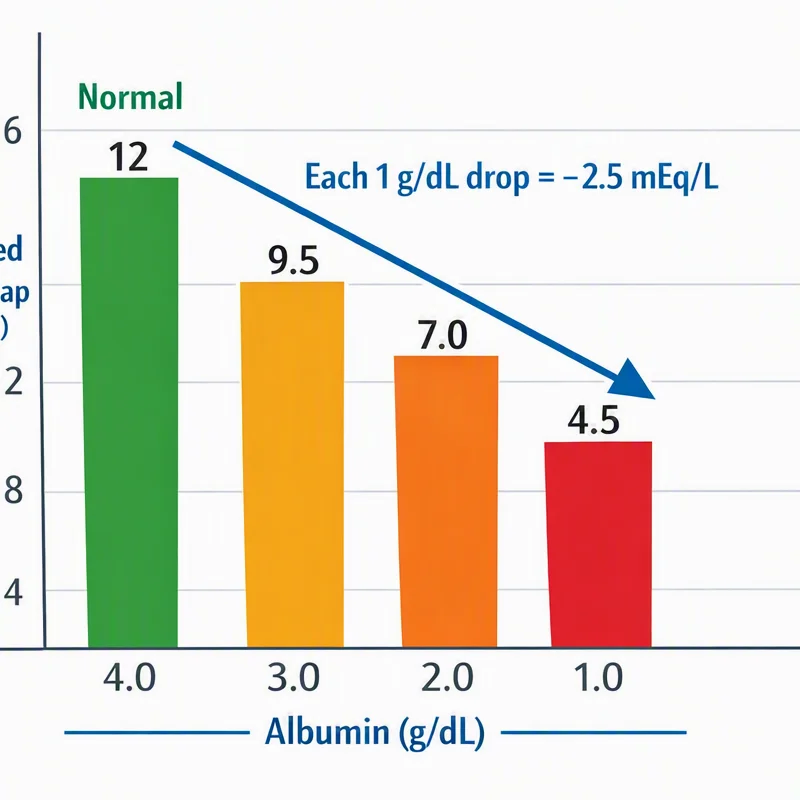
Albumin is one of the key factors affecting the apparent normal range. Because albumin carries negative charge, lower albumin can lower the measured anion gap even when clinically important acids are present. That is why a normal result does not consistently eliminate acid accumulation, especially in patients with hypoalbuminemia.
A thoughtful clinician starts with the reported range as a starting point and then considers whether a corrected anion gap is needed. This is especially important when assessing possible metabolic acidosis in hospitalized patients, where albumin may be reduced and the measured gap can miss part of the true burden of acids.
What causes a high anion gap?
A high anion gap metabolic acidosis often suggests that acids with unmeasured anions have accumulated. Common causes include lactic acidosis, ketoacidosis, renal failure, and toxins. These conditions increase the amount of acids in circulation or reduce the body’s ability to clear them.
In lactic acidosis, lactate goes up when tissues are underperfused, hypoxic, or metabolically stressed. In ketoacidosis, ketones rise when insulin is deficient or carbohydrate use is impaired. In renal failure, acids are retained because kidney excretion is impaired. With certain toxins, the issue may be direct acid generation, toxic metabolites, or altered metabolism.
When the anion gap is high, the next step is more than simply naming the pattern. It is finding the source. That may require measuring lactate, measuring ketones, reviewing the medication and exposure history, and evaluating kidney function. The calculator helps you recognize the pattern; the diagnostic workup explains it.
What causes a typical anion gap metabolic acidosis?
Normal anion gap metabolic acidosis is often called hyperchloremic metabolic acidosis because chloride rises as bicarbonate falls, keeping the calculated gap near typical. A classic cause is intestinal fluid loss, where the body loses bicarbonate through the gastrointestinal tract. Another key cause is renal tubular acidosis, where the kidneys fail to acidify urine or conserve bicarbonate appropriately.
In these situations, the issue is usually loss of bicarbonate rather than accumulation of unmeasured acids. The fall in bicarbonate is https://anion-gap-chart724.iamarrows.com/anion-gap-calculator-for-medical-use-and-assessment offset by a rise in chloride, so the gap may look unremarkable even though the patient is acidemic. This is a common reason why the anion gap should be interpreted with the blood gas analysis and the rest of the chemistry profile.
Recognizing this pattern helps separate gastrointestinal losses from renal acid-handling disorders. That distinction has real clinical implications because treatment differs depending on whether the source is the bowel, the kidney, or both.
How do albumin and the corrected anion gap change interpretation?
Albumin has a strong effect on the anion gap because it contributes a major portion of the body’s negative charge. In hypoalbuminemia, the measured gap can appear artificially low even when there are excess acids present. This is why albumin correction matters in acid-base interpretation.
The idea behind the corrected anion gap is simple: if albumin is low, the expected gap should be adjusted upward to account for the missing negative charge. The exact anion gap correction formula may vary by source, but the goal is the same—avoid underestimating acid burden. This is especially important in critically ill patients, where low albumin can mask clinically significant high-gap disease.
Because albumin reflects protein charge, its reduction changes the balance of measured and unmeasured ions. A normal measured gap in a patient with severe hypoalbuminemia should prompt care. In that setting, the corrected value may reveal occult metabolic acidosis that would otherwise be missed.
What is the delta gap and why does it matter?
The delta gap, also called delta-delta, compares the rise in the anion gap to the fall in bicarbonate. It helps determine whether the patient has only one acid-base problem or a mixed acid-base disorder. This matters because a high anion gap alone does not guarantee a single diagnosis.
Conceptually, the delta gap asks whether the increase in unmeasured acids matches the drop in bicarbonate. If the rise in gap is higher than the fall in bicarbonate, there may be a concurrent metabolic alkalosis or a preexisting low bicarbonate state. If bicarbonate falls more than expected, there may be an additional normal-gap acidosis on top of the high-gap process.
This is why delta-delta analysis is useful in patients with complex illness. For example, someone with ketoacidosis may also have vomiting, renal dysfunction, or diarrhea. The delta gap helps expose that layering so the final diagnosis reflects the complete acid-base picture rather than just the first abnormality seen.
How should an anion gap calculator be used in clinical practice?
An anion gap calculator is most useful as part of a structured diagnostic workflow, not as a one-step conclusion. First, check the basic laboratory values and determine if the patient truly has acidemia or bicarbonate loss. Then interpret the gap in clinical context, including symptoms, hemodynamics, medication use, and possible exposures.
A practical sequence is:
- Check the serum chemistry or basic metabolic panel. Calculate the anion gap from sodium, chloride, and bicarbonate. Check if albumin is low and whether a corrected anion gap is needed. Consult the blood gas analysis or arterial blood gas to confirm the acid-base state. Consider lactate, ketones, kidney function, and exposure history. Look for a mixed acid-base disorder with delta-delta if the pattern seems inconsistent.
This approach is especially helpful in metabolic acidosis evaluation because the anion gap helps identify the cause while the rest of the data show whether the pattern is isolated or mixed. A calculator saves time, but interpretation still depends on clinical reasoning.
Common pitfalls when interpreting the anion gap
One major pitfall is measurement error. If the electrolyte values are inaccurate, the calculated gap will be inaccurate too. Even small analytic differences in chloride or bicarbonate can change the impression. Another pitfall is albumin bias, where low albumin makes the gap appear normal despite significant acid accumulation.
It is also easy to forget about unmeasured ions. The gap is influenced by substances not directly reported on a standard panel, so unusual exposures, paraproteins, or unusual electrolyte shifts can alter the result. Likewise, mixed disorders can hide the expected pattern. A patient may have high-gap acidosis plus metabolic alkalosis, or normal-gap acidosis plus respiratory compensation, making the numbers harder to read.
The safest way of thinking is to view the anion gap as one part of the whole assessment. If the result doesn’t match the patient, re-evaluate the data, repeat labs if needed, and weave in the history rather than making the number to explain the whole story.
When should you order additional tests?
More testing is appropriate when the anion gap suggests a serious cause or when the clinical picture remains unclear. If the gap is high, obtain lactate to assess for lactic acidosis, and obtain ketones when ketoacidosis is possible. If toxic exposure is considered, evaluate the osmolar gap as part of the evaluation for toxic ingestion.
An arterial blood gas is helpful when you need accurate pH, respiratory compensation, and support of the acid-base disorder. This is especially important when the chemistry panel and symptoms do not fit well. In patients with possible renal impairment, the blood gas and chemistry alongside each other can help determine whether the acidosis is metabolic, respiratory, or mixed.
More workup should be driven by the suspected cause. The point is not to request every test for every patient, but to use the anion gap to focus the field and then select targeted studies that clarify the abnormality.
Frequently asked questions about the anion gap
What does a high anion gap mean?
A high anion gap usually means there are extra acids in the blood that are not directly measured on the standard chemistry panel. Common causes include lactic acidosis, ketoacidosis, renal failure, and certain toxins. In practice, it often reflects high anion gap metabolic acidosis and should lead to further evaluation.
How do you calculate the anion gap from lab values?
Apply the anion gap formula: sodium minus the sum of chloride and bicarbonate. Some versions include potassium, but many clinicians omit it. The calculation is usually based on values from a basic metabolic panel or other electrolyte panel.
Why might low albumin affect the anion gap?
Albumin is a anionic protein, so when it is low, the measured anion gap can be reduced than expected. This is why hypoalbuminemia can hide a true gap elevation. Doing albumin correction or a corrected anion gap helps account for that protein charge effect.
What is the delta gap in acid-base diagnosis?
The delta gap, or delta-delta, contrasts the change in anion gap with the change in bicarbonate. It is used to identify a mixed acid-base disorder when one problem may be anion gap in chronic kidney disease hiding another. It is especially valuable when the diagnosis seems more complex than a single metabolic process.
Can a normal anion gap still indicate metabolic acidosis?
Yes. A normal anion gap can still occur in normal anion gap metabolic acidosis, often due to diarrhea or renal tubular acidosis. In those cases, the patient sheds bicarbonate and retains chloride, producing hyperchloremic acidosis without a large gap increase. That is why the anion gap calculator should always be assessed with the full clinical picture.