What Is starvation ketoacidosis?
starvation ketoacidosis is a form of metabolic acidosis that develops when the body is not given enough carbohydrate intake or overall energy intake and starts depending largely on fat for fuel. This shift leads to ketosis, a state in which the liver produces ketone bodies to supply energy. When this process becomes pronounced, acid production builds enough to affect acid-base balance and change laboratory values.
The trigger is usually fasting, prolonged poor intake, or malnutrition. In these situations, the body experiences an energy deficit and a gradual drop in circulating glucose availability. As glucose availability drops, the body increases fat metabolism, which raises ketoacid production. This is different from everyday short-term ketosis because starvation states can produce a clinically meaningful acid-base disturbance.
Starvation ketoacidosis often occurs when nutritional deprivation is severe enough that the liver generates more acidic byproducts than the body can easily buffer. The main ketone-related acids are beta-hydroxybutyrate and acetoacetate. These compounds are part of normal ketone physiology, but in excessive amounts they contribute to metabolic derangement and a recognizable pattern of high anion gap metabolic acidosis.
Understanding this process matters because not all ketosis is the same. In starvation ketoacidosis, the key issue is not simply the presence of ketones, but the combination of glucose depletion, acid generation, and the resulting change in laboratory interpretation. That is why the Anion Gap Calculator can be valuable as a quick tool for clinical interpretation of the lab pattern.
The Reason starvation ketoacidosis Increases the Anion Gap
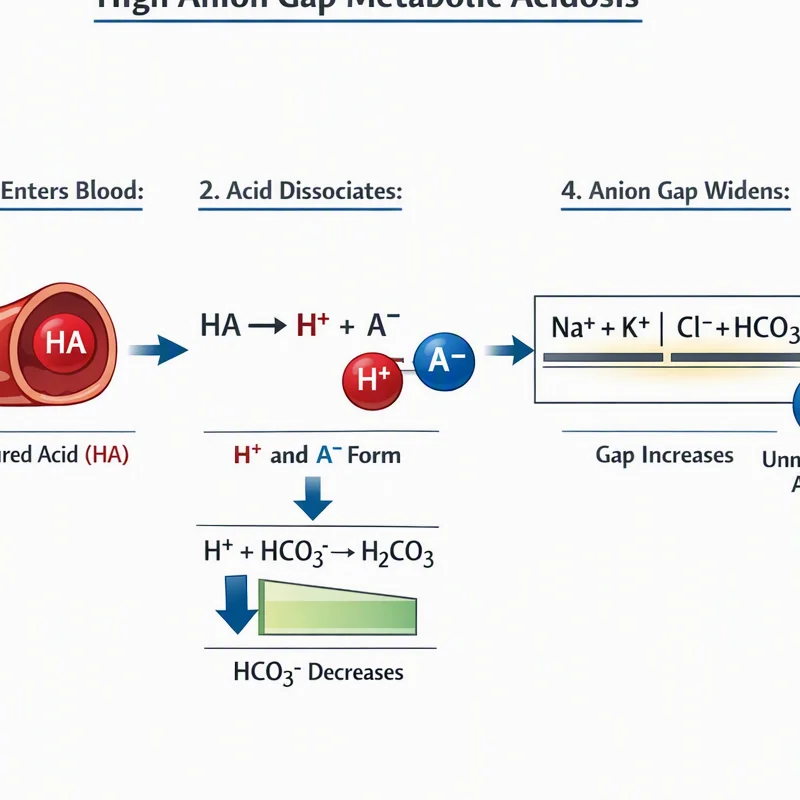
The anion gap rises when acids build up in the blood and their charged components are not directly measured in a standard electrolyte panel. In starvation ketoacidosis, the major cause is the buildup of unmeasured anions formed from ketone bodies. As beta-hydroxybutyrate and acetoacetate accumulate, they consume buffering capacity and leave behind negatively charged acid metabolites that elevate the gap.
This is the classic mechanism of a high-gap acidosis. The body responds to acid buildup by lowering bicarbonate, which is the primary buffer used during acidosis. As bicarbonate falls, the gap often rises because the lost buffer is functionally replaced anion gap in chronic kidney disease by acidic anions that are not directly reflected in routine chemistry values.
The process is driven by ketone accumulation during prolonged fasting or nutritional deprivation. When insulin levels are relatively low and glucose intake is insufficient, the body shifts toward ketone production for fuel. anion gap levels in DKA This adaptive response becomes harmful when ketone generation outpaces utilization and elimination. The resulting organic acids shift acid-base balance and produce the elevated anion gap seen on labs.
Although both ketone bodies contribute, beta-hydroxybutyrate is often the dominant acid in more significant ketoacid states. Acetoacetate also contributes to the measured acid load, but the total burden depends on severity, duration, and physiologic stress. The important point is that the ketones function as organic acids, and their presence explains why starvation ketoacidosis is a true cause of anion gap calculation abnormalities rather than a benign lab curiosity.
Put simply: starvation creates an energy shortage, the body burns fat, fat metabolism yields ketones, and those ketones act as unmeasured acids. That chain of events is why the anion gap rises.
How to Calculate and Understand the Anion Gap
An Anion Gap Calculator can help estimating whether the electrolyte profile indicates a elevated-gap acidosis. The usual calculation relies on sodium, chloride, and bicarbonate:
Anion gap = sodium - (chloride + bicarbonate)
This calculation is easy to use, but how you interpret it depends on the complete clinical picture. A elevated result may indicate an excess of unmeasured anions, while a result within the normal range makes starvation ketoacidosis less suspected or indicates an earlier / milder stage. Because lab reference ranges vary, the exact cutoff should be read alongside the local lab values and the patient’s general condition.
In starvation ketoacidosis, the gap increases because bicarbonate is consumed to buffer the acids generated by ketogenesis. The low bicarbonate often tracks the extent of acidosis. At the same time, chloride may appear relatively normal or may increase in mixed patterns depending on volume status and replacement fluids. Sodium is needed for the calculation and may also change with dehydration, poor intake, or concurrent illness.
When relying on an Anion Gap Calculator, it can help to think in terms of clinical interpretation rather than a single value. A somewhat elevated gap may still be important if the patient has clear malnutrition, nausea and vomiting, poor food intake, or visible ketosis. A extremely high value suggests a more intense metabolic acidosis or another additional cause of high anion gap metabolic acidosis.
For interpreting the result effectively, pair the gap with the rest of the laboratory findings:
- Sodium: helps anchor the overall calculation and judge hydration or dilutional effects. Chloride: helps clarify whether the acidosis is accompanied by secondary or mixed changes. Bicarbonate: typically decreases as acid load increases and is a key marker of how severe it is.
The calculation represents just one piece of the whole picture. The aim is not just to detect an abnormal number, but to link it to the typical pattern of ketone buildup, pH disturbance, and the likely cause of the metabolic abnormality.
Characteristic Lab Results in Starvation Ketoacidosis
Starvation ketoacidosis has a recognizable laboratory profile, although the exact presentation varies depending on the duration of fasting, degree of malnutrition, and any underlying illness. The most helpful tests often include serum glucose, electrolytes, arterial blood gas, and serum ketones.
Serum glucose is frequently within normal limits or low rather than markedly elevated. This remains a key clue separating starvation ketoacidosis from other forms of ketoacidosis. Because the underlying problem is insufficient intake rather than excess glucose, the glucose level may reflect reduced stores rather than hyperglycemia.
Electrolytes often show the biochemical signature of acid-base stress. The bicarbonate level is usually low, supporting the diagnosis of metabolic acidosis. Sodium and chloride may vary depending on fluid losses, vomiting, dehydration, or treatment before testing. Reviewing the full panel of serum electrolytes helps determine whether the picture is isolated or mixed.
Serum ketones are typically positive, and if quantitative testing is available, elevated beta-hydroxybutyrate supports the diagnosis more strongly than a basic urine ketone screen alone. This is because urine ketone testing may underrepresent the burden of beta-hydroxybutyrate. In starvation states, beta-hydroxybutyrate can be disproportionately elevated and is a major driver of the acid load.
An arterial blood gas may show acidemia with a low bicarbonate and compensatory respiratory changes. A patient may develop compensatory hyperventilation as the body tries to lower carbon dioxide and offset the acid load. This respiratory response helps maintain pH, but it does not correct the underlying problem.
Findings often include:
- Low or normal serum glucose Low bicarbonate Positive serum ketones Elevated beta-hydroxybutyrate and acetoacetate Abnormal electrolytes Acid-base changes on arterial blood gas
These findings support the diagnosis, but they also help estimate severity. The more pronounced the acidosis and ketone burden, the more likely the anion gap is to be clearly elevated.
How It Differs Against Diabetic Ketoacidosis and Other Causes
Starvation ketoacidosis can appear similar to other causes of high anion gap metabolic acidosis, so separating it from related conditions is essential. The closest mimic is diabetic ketoacidosis, but there are several differences.
In diabetic ketoacidosis, the core issue is insulin deficiency, which drives severe ketone production and usually produces far higher glucose levels. Starvation ketoacidosis, by contrast, is driven by glucose depletion and inadequate intake. The patient may have usual or low glucose rather than marked hyperglycemia. That distinction changes both the diagnostic thinking and treatment priorities.
Alcoholic ketoacidosis is another key differential. It often occurs after poor intake combined with heavy alcohol use and may share features of starvation physiology. Like starvation ketoacidosis, it can produce ketone-related acids and an elevated anion gap. The broader context, however, differs, and alcohol use can add extra metabolic complexity.
Lactic acidosis is another major cause of anion gap elevation. Instead of ketone bodies, lactate is the main unmeasured anion. Lactic acidosis may occur with tissue hypoperfusion, sepsis, or other forms of metabolic stress. If lactate is elevated, it can explain part or all of the gap, even if ketosis is present at the same time.
Renal failure can also raise the gap because failing kidneys cannot clear acids effectively. In that setting, retained acids and other retained solutes contribute to the anion gap. Renal impairment can coexist with starvation or dehydration, which makes interpretation more challenging and reinforces the need for thorough diagnostic evaluation.
The key differences often come down to the pattern of labs and the clinical story:
- Diabetic ketoacidosis: usually marked hyperglycemia and insulin deficiency Starvation ketoacidosis: fasting, malnutrition, low or normal glucose, ketone-driven acidosis Alcoholic ketoacidosis: alcohol use plus poor intake, overlapping metabolic features Lactic acidosis: elevated lactate from hypoperfusion or stress Renal failure: impaired acid clearance and retained metabolic acids
Because these conditions can overlap, the best approach is to use the anion gap as a beginning point, not the final diagnosis. The gap identifies the presence of excess unmeasured anions, but only the rest of the clinical picture can establish the cause.
When a High Anion Gap Requires Immediate Evaluation
A high anion gap consistently merits attention, but the level of concern depends on the severity, associated symptoms, and the complete acid-base disorder. Starvation ketoacidosis may be slight in some cases, but it can still become dangerous if the patient is fluid depleted, not able to eat, or has another illness contributing to the metabolic disturbance.
Urgent evaluation is important when symptoms suggest worsening acidosis or systemic illness. These may include mental status changes, marked weakness, persistent vomiting, increased respiratory rate, dehydration, or inability to sustain oral intake. A patient with clear acidemia on an arterial blood gas and an higher gap needs prompt clinical assessment rather than basic observation.
The concern is not only the ketones themselves, but the larger acid-base balance. If bicarbonate continues to fall, the acidosis can intensify. If the patient has concurrent infection, vomiting, renal impairment, or significant volume depletion, the metabolic picture can worsen quickly.
Helpful considerations during assessment include:
- The duration for which the patient has had reduced intake or fasting Whether there is malnutrition or ongoing poor nutrition Evidence of ketosis or marked ketone burden Whether serum glucose is below normal, normal, or increased Whether another cause of high anion gap metabolic acidosis may also be present
If the patient is symptomatic or the laboratory values show a substantial metabolic derangement, the issue should be treated as more than a simple electrolyte abnormality. The elevation in the anion gap is a marker of underlying acid production, and the reason for that acid load must be identified.
Frequently Asked Questions About Starvation Ketoacidosis and Anion Gap
Can starvation ketoacidosis consistently cause a raised anion gap?
Not in every case, but it often does. ketoacidosis from starvation typically raises the anion gap because ketone-related acids create unmeasured anions. In initial or mild cases, the gap may be only slightly elevated or even appear almost normal if the acid load is minimal or if other electrolyte changes are present. The overall medical context and anion gap interpretation count as much as the number itself.
How high is the anion gap in starvation ketoacidosis?
The amount of elevation varies with the severity of ketosis, duration of fasting, and presence of other illnesses. Some cases show a mild to moderate rise, while more severe starvation ketoacidosis can produce clear high anion gap metabolic acidosis. The exact level is secondary than whether the result aligns with the rest of the picture, including bicarbonate, serum glucose, and ketone testing.
What lab tests are useful to confirm ketoacidosis from starvation?
The most helpful tests include serum glucose, electrolytes, arterial blood gas, and serum ketones. Quantitative beta-hydroxybutyrate is especially helpful because it reflects the main ketone burden better than some urine tests. These results, combined with the history of reduced intake or malnutrition, support the diagnosis.
How is starvation ketoacidosis different from diabetes-related ketoacidosis?
Diabetic ketoacidosis is driven by insulin deficiency and usually presents with markedly elevated glucose levels. Starvation ketoacidosis is caused by glucose depletion from inadequate intake and often has low or low serum glucose. Both can produce ketosis and elevated anion gap acidosis, but the trigger, lab pattern, and treatment approach differ.
Can the anion gap normalize to baseline after therapy?
Absolutely. Once the underlying cause is addressed, ketone production falls, unmeasured anions lessen, and the anion gap can return toward typical values. Management usually targets the energy deficit, fluid balance, and electrolyte abnormalities, which helps maintain acid-base balance. Subsequent laboratory values are often used to confirm improvement in metabolic acidosis and overall clinical status.
Starvation ketoacidosis is a real acid-base disorder, not just a harmless ketotic state. The key pattern is the rise in the anion gap from ketone-related organic acids, especially beta-hydroxybutyrate and acetoacetate, during periods of fasting or malnutrition. An Anion Gap Calculator helps you spot that pattern rapidly, but the most accurate interpretation always comes from pairing the calculation with the clinical story, laboratory values, and thoughtful medical assessment.