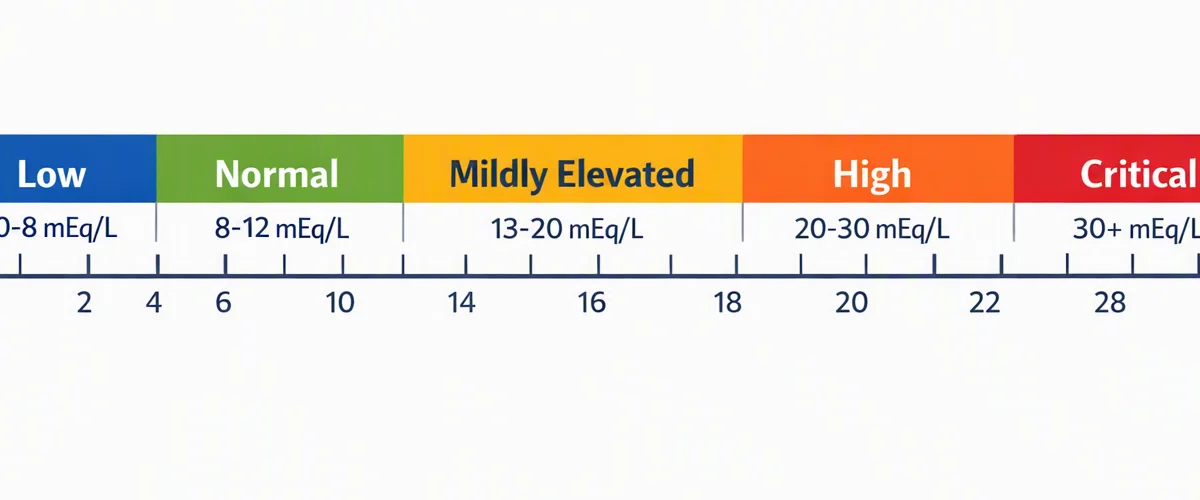
Why the anion gap Measures
The anion gap is a computed value that assists clinicians assess metabolic acidosis and other changes in electrolytes. It reflects the difference between typically measured cations and anions in the blood, mainly using the electrolyte panel. In practice, the anion gap is a valuable shortcut for identifying whether unmeasured acids may be building up in the body.
An anion gap calculator streamlines this process by converting the available lab values into a single number that enhances diagnostic interpretation. Because the calculation depends on measured ions rather than direct acid detection, it functions as a marker of acid-base balance rather than a diagnosis by itself.
Most often, the anion gap is used to help distinguish high anion gap metabolic acidosis from normal anion gap metabolic acidosis. A high value may indicate the presence of organic acids such as lactate or ketones, while a normal value may imply bicarbonate loss or impaired renal handling of acid. The result should always be considered with the full clinical context and not as an isolated finding.
How to Use an Anion Gap Calculator
An anion gap calculator generally requires three inputs: serum sodium, serum chloride, and serum bicarbonate. These measurements are taken from standard serum electrolytes testing. When the data is entered, the calculator applies the standard calculation formula:
Anion gap = serum sodium - (serum chloride + serum bicarbonate)Some calculators may also account for potassium, but the most widely used clinical version excludes it. The reason this formula works is that measured sodium represents cation, while chloride and bicarbonate are the principal measured anions. The gap represents unmeasured ions, including albumin and other negatively charged proteins, organic acids, and various solutes.
To use the calculator correctly, ensure the lab values are from the same draw if possible. Differences in timing can influence the result, especially if the patient has a changing acid-base status. A single number should be read alongside symptoms, medication use, renal function, and other laboratory findings.
What Makes Albumin Affects the Anion Gap
Albumin serves as one of the most important unmeasured anions in blood. Because it carries a negative charge, it contributes significantly to the anion gap. When serum albumin is low, the reported anion gap can appear falsely normal or slightly elevated, even when a real acid-base problem exists.
This is why hypoalbuminemia matters so much in clinical interpretation. If a patient has low albumin, the body has less negatively charged proteins to support the gap. That reduction can obscure metabolic acidosis, especially in very sick patients where the acid burden may be marked.
calculate AG with potassiumThe effect is tied to protein charge. As albumin falls, the body may respond with increased chloride levels or other shifts in serum electrolytes to preserve electroneutrality. The result is a reduced apparent gap, even if unmeasured acids are present. This is the reason albumin correction is often needed for more accurate assessment.
Albumin-Corrected Anion Gap Equation
The albumin-based corrected gap recalculates the initial gap to factor in low blood albumin. A common adjustment formula is:
Corrected anion gap = measured anion gap + 2.5 × (4.0 - albumin in g/dL)In this approach, normal albumin is typically considered 4.0 g/dL. For each 1 g/dL drop below normal, the anion gap is raised by about 2.5 mEq/L. This compensation factor reflects the contribution of albumin to the value and helps uncover a hidden high gap.
For example, if the measured gap is 10 and albumin is 2.0 g/dL, the corrected value becomes 10 + 2.5 × 2 = 15. That may move the result from a seemingly unremarkable range into a more suspicious one. This is why albumin correction can change both diagnosis and treatment decisions.
Many tools pair the basic calculator with albumin correction so the clinician can see both the original and revised values. That dual view improves clinical utility, especially when the patient has low albumin from illness, inflammation, or poor nutrition.
Interpreting Normal, High, and Low Anion Gap Results
A normal anion gap is usually interpreted using the lab’s normal range, which can differ by method and institution. In broad terms, a normal result suggests that the balance between measured cations and anions is in the expected range. However, a normal value does not by itself exclude acid-base disturbance, especially if albumin is low or if there are mixed disturbances.
A increased anion gap metabolic acidosis suggests accumulation of unmeasured acids. This pattern is commonly linked to lactate, ketones, and retained acids in kidney dysfunction. It often calls for further testing for the underlying cause.
A reduced anion gap is less common and is often overlooked. It may occur when albumin is low, when there is excess positively charged protein, or when there is an analytical problem. Although a low value is not always dangerous, it should not be ignored because it can reveal important underlying disease or error.
Common Causes of Elevated Anion Gap
One of the most important causes of an elevated anion gap is lactic acidosis. In this condition, lactate builds up when oxygen delivery or consumption is compromised. Bloodstream infection, shock, severe hypoperfusion, and certain medications can all contribute. As lactate is an unmeasured anion, the gap rises as its concentration builds.
Ketoacidosis is an additional classic cause. In diabetic ketoacidosis, starvation ketosis, or alcoholic ketoacidosis, ketones rise and increase the gap. In these settings, the acid burden may be significant even before the bicarbonate level falls dramatically.
Renal insufficiency can also result in elevated values because the kidneys cannot eliminate acids normally. With worsening declining renal function, acids accumulate and bicarbonate may drop. This is one reason the anion gap is often reviewed alongside creatinine, blood urea nitrogen, and the overall metabolic profile.
Additional causes may include toxins, medications, and mixed disorders. Still, lactic acidosis, ketoacidosis, and renal failure remain among the most relevant explanations for a high result.
Frequent Sources of a Decreased Anion Gap
The first cause to consider is lab error. A minor measurement issue in sodium, chloride, or bicarbonate can substantially alter the calculated value. If the result seems inconsistent with the clinical picture, repeating the test is often a useful first step.
Hypoalbuminemia is one of the most common true causes of a low anion gap. Because albumin is a major unmeasured anion, a low level reduces the apparent gap. This makes albumin correction very important when reviewing an electrolyte panel in hospitalized or chronically ill patients.
Paraproteinemia can also lower the gap. In conditions with excess positively charged proteins, such as some monoclonal gammopathies, the measured balance changes. The body may appear to have fewer unmeasured anions because the abnormal proteins alter the electrical distribution. A low gap in this setting can be a clue that deserves additional workup.
In rarer cases, certain medications or analytical interferences can contribute. However, in routine practice, lab error, hypoalbuminemia, and paraproteinemia are the main considerations.
When to Use Albumin Correction in Day-to-Day Care
Albumin correction is most useful in critical care, where patients often have complex acid-base disorder patterns and low serum albumin. In this setting, relying on the uncorrected number alone can fail to detect a meaningful elevation in the gap. That matters because treatment may depend on identifying the true source of acidosis.
It is also helpful when a patient has sepsis, malnutrition, liver disease, nephrotic syndrome, or fluid overload, all of which may reduce albumin. In these cases, the corrected result provides better clinical interpretation than the raw number. It can also help distinguish a truly normal gap from a masked high gap state.
As a practical rule, if albumin is below normal and the clinical concern is unexplained acidosis, correction should be seriously considered. The calculator becomes more valuable when it is used as part of a more complete assessment rather than as a standalone metric.
Limitations of the Anion Gap Calculator
Even a well-designed anion gap calculator has limits. The biggest is the dependence on the lab’s reference range and analyzer method. Different measurement platforms can yield different baseline values, so what looks abnormal in one system may be acceptable in another.
Measurement error can also affect the result. Small inaccuracies in serum sodium, serum chloride, or serum bicarbonate can shift the calculation noticeably. In addition, not all causes of acidosis create a high gap, and mixed disorders can blur the pattern.
Clinical context remains essential. A normal or corrected value does not exclude illness, and a high value does not identify the cause by itself. The result should always be interpreted with symptoms, vital signs, kidney function, lactate, ketones, medication exposure, and overall clinical interpretation. The calculator is best viewed as a decision-support tool, not a replacement for judgment.
FAQ About the Anion Gap Calculator
What does an anion gap calculator used for?
An anion gap calculator is designed to estimate the anion gap from basic lab values and support the assessment of metabolic acidosis. It is especially valuable for identifying high anion gap metabolic acidosis and for aiding clinical interpretation of an abnormal electrolyte panel.
How do you correct the anion gap for albumin?
Albumin correction is usually done by adding about 2.5 mEq/L to the measured anion gap for each 1 g/dL of albumin below normal albumin of 4.0 g/dL. This produces an albumin-corrected anion gap that more closely represents the true acid-base status when hypoalbuminemia is present.
Why can low albumin affect the anion gap?
Serum albumin carries negative protein charge and makes a major contribution to the gap. When albumin is low, fewer unmeasured anions are present, so the measured value may fall even if the patient still has an underlying acid burden. This can make the gap look closer to normal than it really is.
What does a high anion gap mean?
A high result often indicates metabolic acidosis from unmeasured acids such as lactate or ketones. Common causes include lactic acidosis, ketoacidosis, and renal failure. The exact meaning depends on the patient’s history, other labs, and overall clinical context.
Is it possible to have metabolic acidosis?
Yes. A normal anion gap can still occur with normal anion gap metabolic acidosis, such as bicarbonate loss states. It can also appear normal when hypoalbuminemia masks a true elevation, which is why albumin correction is important for accurate anion gap interpretation.