Why this calculator is and its importance
An anion gap is a derived value that assists clinicians and patients determine whether an acid-base balance problem may be present, especially when evaluating metabolic acidosis. An anion gap calculator uses common electrolytes from a serum chemistry panel to estimate whether there are unmeasured acids in the blood. This makes it valuable in metabolic acidosis evaluation, where the goal is to find the cause of acid accumulation and guide the diagnostic workup.
The result is not a diagnosis by itself. Instead, it is a tool for clinical interpretation of laboratory values. A calculated gap can suggest whether the issue is likely a high anion gap metabolic acidosis or a normal anion gap metabolic acidosis. That distinction matters because it alters what conditions are most likely, which tests come next, and how urgently a patient may need assessment.
In the setting of kidney dysfunction, this calculation becomes especially important. Uremic acidosis can develop when declining renal function leads to retention of acids. As uremia progresses, acid handling worsens, and the anion gap may rise. For that reason, an anion gap calculator is a useful way to help interpret the biochemical pattern seen in kidney failure or chronic kidney disease.
Understanding the anion gap also helps distinguish between different causes of electrolyte imbalance. Some disorders lower bicarbonate without increasing the gap, while others create excess unmeasured anions. Using the calculator does not replace judgment, but it does give a fast, organized starting point for patient assessment.
How to calculate the anion gap
The basic anion gap formula relies on the measured levels of sodium, chloride, and bicarbonate. The most commonly used equation is:
Anion gap = sodium - (chloride + bicarbonate)
Because these lab values are regularly available from a serum chemistry panel, the calculation is simple to perform. The equation estimates the difference between the major measured cations and anions in plasma. That difference represents unmeasured ions, including certain acids and proteins.
Different laboratories may report slightly different reference range values depending on their analyzers and whether potassium is included. In many clinical settings, the reported range is interpreted with potassium omitted, and the result is compared with local laboratory values rather than a single universal cutoff.
When you calculate anion gap, the key is not just the number but the context. A slightly elevated result can be meaningful if the patient has symptoms or other findings that support an acid-base disorder. Likewise, a normal result does not completely exclude a problem if there is mixed pathology or if the patient has hypoalbuminemia.
The calculator is especially helpful when paired with serum bicarbonate and a blood gas. That combination helps confirm whether there is true metabolic acidosis and whether respiratory compensation is present. In other words, the anion gap is only one anion gap in chronic kidney disease part of the overall clinical picture.
Exploring uremic acidosis
Uremic acidosis is a form of acid buildup that occurs when impaired kidneys can no longer remove acid effectively or regenerate enough bicarbonate. It is closely linked to uremia, the buildup of waste products in the blood due to poor kidney filtration. When renal function declines, acid retention increases and the body’s buffering systems become overwhelmed.
This problem is commonly seen in advanced kidney failure and can also appear in chronic kidney disease as the disease progresses. The acids involved may include organic acids and other retained solutes that contribute to an increased anion gap. Over time, the pattern can evolve, and patients may show overlapping features of high-gap and normal-gap acidosis depending on the stage and cause of renal impairment.
In diagnostic terms, uremic acidosis is part of the broader category of renal insufficiency-related acid-base disorders. The presence of a high anion gap may support the idea that reduced filtration is allowing acid accumulation, but it should still trigger a broader assessment for other causes. Kidney function tests, serum bicarbonate, and blood gas analysis help clarify whether the patient has isolated metabolic acidosis or a more complex disorder.
In clinical practice, the uremia diagnosis is not made by the anion gap alone. Instead, clinicians combine symptoms, lab results, and the overall pattern of kidney dysfunction. The calculator helps identify a likely acid-base disorder, while the rest of the workup determines why it is happening and how severe it may be.
Normal compared with increased anion gap in clinical analysis
A typical anion gap often indicates that bicarbonate has been lost and substituted by chloride, which is why this pattern is often called a non-anion-gap acidosis. In contrast, a elevated anion gap metabolic acidosis indicates that unmeasured acids are building up in the bloodstream. This is a major distinction in clinical assessment because it limits the differential diagnosis.
To interpret the number accurately, clinicians also consider albumin, the most abundant negatively charged protein in plasma. Albumin accounts significantly to the measured gap, so low levels can make the gap appear deceptively normal. This means acid-base balance cannot always be assessed from the raw number alone.
A truly elevated gap often reflects added organic acids or retained toxins. In kidney dysfunction, the increased gap can reflect accumulation of acids that are no longer cleared properly. That makes the anion gap helpful for distinguishing uremic acidosis from other acid-base disorders, especially when paired with serum bicarbonate and blood gas data.
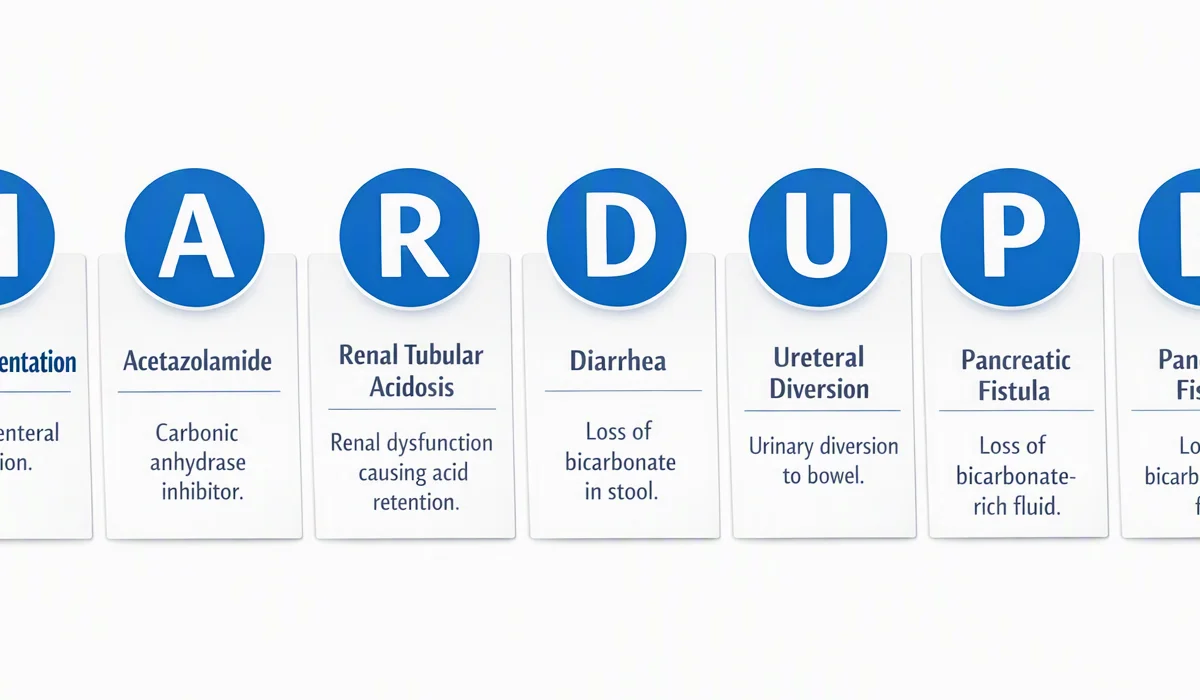
A normal gap does not rule out clinically important illness. It may point to a different process, such as diarrhea-related bicarbonate loss or renal tubular issues. By comparison, an increased gap points toward a different diagnostic pathway, including toxin exposure, lactic acid buildup, ketoacidosis, and renal failure.
Typical causes of high anion gap metabolic acidosis
Several conditions can cause high anion gap metabolic acidosis. The primary causes to consider include lactic acidosis, ketoacidosis, toxins, and renal failure. Each produces acid accumulation through a different mechanism, but the end result is similar: increased unmeasured anions and a higher gap.
Lactic acidosis develops when lactate builds up due to poor tissue oxygen delivery, severe infection, anion gap diagnostic for ethylene glycol shock, seizures, or other states of stress. This remains an important differential diagnosis because lactate is an organic acid and can sharply increase the gap.
Ketoacidosis arises when ketone bodies accumulate, most often in uncontrolled diabetes, prolonged fasting, or heavy alcohol use. Ketones are acidic and contribute to the gap. In the right clinical context, this can be a medical emergency.
Toxins are an additional major group. Certain ingestions can produce a profound increased anion gap and may require urgent treatment. The history, symptoms, and timing of exposure are useful clues during patient assessment.
Renal failure is particularly important in uremic acidosis because failing kidneys cannot clear acid efficiently. This results in retention of sulfuric and phosphoric acids and other unmeasured solutes. In advanced chronic kidney disease, this pattern is often part of the broader metabolic acidosis picture.
Because multiple causes can coexist, clinicians often use the anion gap alongside other laboratory values and the blood gas to sort out the diagnosis. The calculator helps identify the pattern, but the cause still depends on the whole clinical story.
How low albumin affects anion gap results
Hypoalbuminemia may substantially change an anion gap result because albumin is a major unmeasured anion in plasma. When albumin is low, the gap may look lower than expected even when acid accumulation is present. This is why albumin correction plays a role in many patients, especially those with chronic illness or kidney disease.
The concept is clear: less albumin means fewer negatively charged protein molecules affecting the gap. Without correction, a true high-gap disorder may be missed or underestimated. That can affect laboratory interpretation and postpone identifying an acid-base disorder.
The corrected anion gap is therefore more useful than the raw value when albumin is low. Clinicians often adjust the result based on the patient’s albumin level so they can better estimate the real degree of unmeasured acid burden. This is especially important in uremic acidosis, where kidney disease and poor nutritional status may coexist.
Albumin correction increases the accuracy of the diagnostic workup, but it still requires context. A corrected value should be interpreted with the patient’s symptoms, blood gas, kidney function tests, and serum bicarbonate. In other words, correction helps sharpen the picture; it does not replace broader clinical interpretation.
How to operate the calculator step-by-step
Working with an anion gap calculator is simple if you have the right lab values. The most important inputs are serum sodium, serum chloride, and serum bicarbonate from the chemistry panel. When those numbers are available, the calculation is immediate.
Step 1: Confirm the patient’s electrolyte values. Make sure the measurements come from the same sample and that they reflect current laboratory values.
Step 2: Use the anion gap formula: sodium minus the sum of chloride and bicarbonate.
Step 3: Contrast the result with the lab’s reference range and assess whether the value is normal or increased.
Step 4: If albumin is low, consider whether an albumin correction is needed to avoid underestimating the gap.
Step 5: Interpret the result in the setting of the patient’s symptoms, kidney function, and blood gas findings.
Below is a simple calculation example: if serum sodium is 140, serum chloride is 100, and serum bicarbonate is 16, then the gap is 140 - (100 + 16) = 24. That would generally be considered an increased anion gap, depending on the laboratory’s range. If albumin is low, the corrected result may be more informative.
This process helps clinicians interpret anion gap results promptly and uniformly. It is especially helpful during a metabolic acidosis evaluation, when the main question is whether the acidosis is due to bicarbonate loss or increased acid production/retention.
When to get clinical evaluation
Although the anion gap calculator is useful, it should not replace medical evaluation when concerning findings are present. Symptoms such as shortness of breath, confusion, severe fatigue, vomiting, deep rapid breathing, chest discomfort, or reduced urine output may suggest a significant acid-base disorder.
Those with known kidney disease should get medical care if they develop increasing weakness, swelling, queasiness, or uremic symptoms. These may indicate reduced kidney function and suspected uremic acidosis. A provider may request a blood gas, repeat electrolyte tests, and renal function tests to assess severity.
Urgent care matters most when symptoms are severe, abrupt, or accompanied by dehydration, an infectious illness, suspected exposure to toxins, or changes in mental status. A blood gas can clarify whether the patient truly has a metabolic acidosis and whether it is compensated for or mixed with another disorder.
Because acid-base problems may progress quickly, clinical assessment should be swift when the laboratory pattern is markedly abnormal or the patient appears ill. The anion gap is a important screening and interpretation tool, but the underlying cause determines the immediacy and treatment approach.
FAQ about anion gap and uremic acidosis
What is an anion gap calculator used for in uremic acidosis?
An anion gap calculator is used to estimate whether a patient has a elevated anion gap pattern that may fit uremic acidosis. It helps clinicians evaluate metabolic acidosis, interpret laboratory values from a serum chemistry panel, and determine whether kidney dysfunction may be causing acid retention. In uremic acidosis, the calculator aids clinical interpretation but does not substitute for a full diagnostic workup.
What is the formula for calculating the anion gap?
The standard anion gap formula is sodium minus the sum of chloride and bicarbonate. In equation form, it is: anion gap = sodium - (chloride + bicarbonate). Some laboratories use slightly different methods or factor in potassium, so the result should always be interpreted using the reference range used by the lab and the patient’s full clinical picture.
How does kidney failure cause a high anion gap?
Kidney failure limits the body’s ability to excrete acid and maintain normal acid-base balance. As renal function declines, acids and unmeasured anions accumulate, which increases the anion gap and can lead to metabolic acidosis. This is why chronic kidney disease and advanced renal insufficiency are common settings for uremic acidosis and elevated anion gap findings.
Do you need to correct the anion gap for low albumin?
Absolutely, in many cases. Reduced albumin can cause the anion gap appear falsely normal because albumin is a primary negatively charged plasma protein. Albumin correction improves refine laboratory interpretation and can show a corrected anion gap that better represents the true acid-base disorder. This is especially important when hypoalbuminemia is observed.
What conditions can cause a high anion gap besides uremic acidosis?
Various conditions can cause high anion gap metabolic acidosis besides uremic acidosis. Frequent causes include lactic acidosis, ketoacidosis, toxin exposure, and renal failure. Other diagnostic possibilities may be considered depending on the patient’s symptoms, blood gas findings, and electrolyte pattern. A complete clinical assessment is needed to determine the exact cause.