What exactly is the Anion Gap?
The anion-gap value is a helpful way to assess electrolytes and explain the balance between measured and unmeasured anions in the blood. It is usually obtained from a serum chemistry panel and assists clinicians narrow the differential diagnosis for acid-base issues, especially metabolic acidosis.
From a pathophysiology standpoint, the anion gap reflects the disparity between the main detecting ethylene glycol with AG measured cations and anions in serum. Because routine testing does not directly measure every ion, the calculated value suggests the amount of unmeasured ions available. This makes the anion gap a useful tool for clinical interpretation and laboratory assessment when evaluating an acid-base disturbance.
Medical students often first encounter the anion gap as part of a broader serum chemistry or electrolyte panel. It is especially important because a change in the gap can reveal a hidden metabolic derangement even when the pH has not yet been reviewed. In other words, the anion gap is not just a number; it is a signal to the underlying acid-base balance.
How to Determine the Anion Gap
The anion gap formula is often expressed as:
Anion gap = sodium − (chloride + bicarbonate)In this formula, sodium is the chief measured cation, while chloride and bicarbonate are the anions that are measured. An anion gap calculator simply automates this math from the lab values you enter, helping minimize arithmetic errors during a busy clinical workflow.
It is simple to use the calculator:
- Input the serum sodium value. Enter the serum chloride value. Type in the serum bicarbonate value. The calculator returns the anion gap and often indicates whether it is elevated or within the expected reference interval.
For instance, if sodium is 140, chloride is 104, and bicarbonate is 24, the anion gap is 12. In many laboratories, this is regarded as normal. The exact interpretation depends on the lab’s reporting method and local reference range, so students should always compare the result with the values provided by the institution.
It is important to understand the formula because the result is only as reliable as the underlying data. If any value is inaccurate due to a measurement error, the calculated anion gap may be misleading. That is why clinicians should always interpret the output in the context of the broader electrolyte disorder and the patient’s clinical picture.
Typical Interval and Albumin Correction
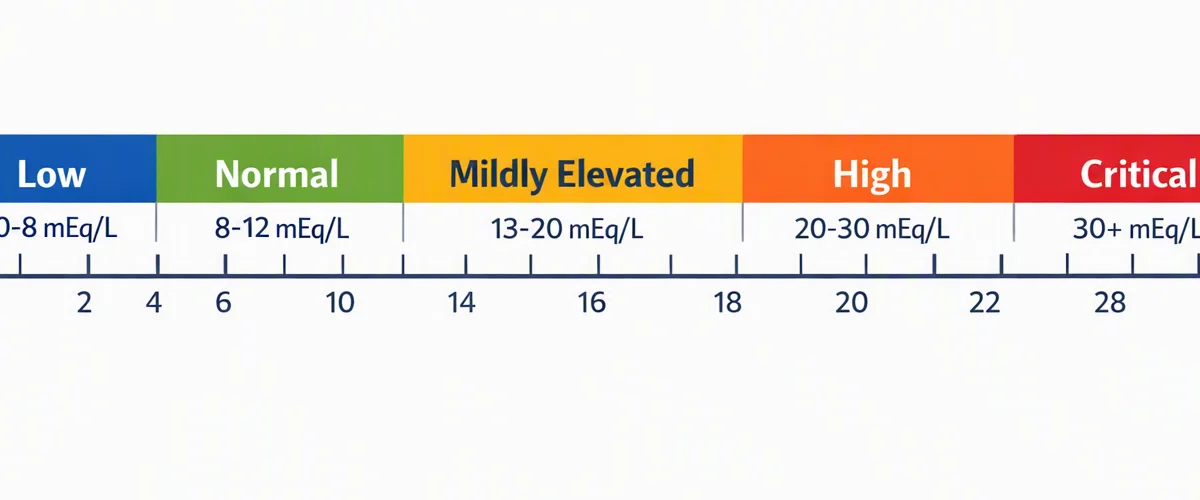
A normal anion gap is usually defined by the laboratory’s reference range, which may vary depending on the analyzer and whether potassium is included in the equation. A common potassium-free reference interval is roughly 8 to 12 mEq/L, but this should never replace the local lab standard.
One of the most essential adjustments in real practice is the effect of albumin. Because albumin is a major unmeasured anion, hypoalbuminemia can make the anion gap appear artificially low or normal even when an acid load is present. This is why albumin correction is often crucial for accurate interpretation.
A practical way to think about it: when albumin falls, the measured anion gap falls too, because fewer negatively charged proteins are contributing to the total. A corrected result helps uncover an elevated gap that might otherwise be missed. In many teaching settings, a commonly used correction is to add approximately 2.5 mEq/L to the anion gap for every 1 g/dL decrease in albumin below 4 g/dL. However, students should follow local teaching standards and institutional methods.
This is especially important in hospitalized patients, where hypoalbuminemia is common. Without albumin correction, clinicians may downplay the severity of metabolic acidosis. A apparently normal result on an anion gap calculator does not always mean the acid-base picture is normal.
Clinical Interpretation of an Elevated Anion Gap
An high anion gap indicates the existence of excess acids or additional unmeasured ions in the serum. This pattern is commonly seen in high anion gap metabolic acidosis, a central topic in acid-base physiology. In this scenario, the body retains acids, and bicarbonate is depleted as buffering occurs.
Common causes include lactic acidosis, ketoacidosis, and uremia. Each has a distinct pathophysiology, but all can produce a unexpectedly high gap:
- Lactic acidosis: elevated lactate from tissue hypoperfusion, sepsis, severe exercise, or impaired lactate clearance. Ketoacidosis: accumulation of ketone bodies in diabetic, alcoholic, or starvation states. Uremia: retention of acids in advanced kidney failure, contributing to the burden of unmeasured anions.
When the gap is increased, the next step is not merely to identify the disorder. Students should ask why the acid is present, how marked the derangement is, and whether there are further abnormalities. The anion gap helps with diagnostic approach, but it is only one part of the puzzle.
For example, a patient with vomiting, altered mental status, and elevated glucose may have ketoacidosis. Another patient with hypotension and rising lactate may have lactic acidosis. A third patient with renal failure and elevated creatinine may have uremia. In each case, the same calculator output requires distinct clinical interpretation.
Causes of a Regular Anion Gap Metabolic Acidosis
Not every metabolic acidosis causes an high gap. Normal anion gap metabolic acidosis, also called non-anion gap metabolic acidosis, occurs when bicarbonate is lost or chloride increases to maintain electroneutrality. In this pattern, the anion gap remains in the expected range even though the patient is acidotic.
Two major causes are diarrhea and renal tubular acidosis. With diarrhea, the gastrointestinal tract loses bicarbonate, producing loss of bicarbonate and a decrease in serum bicarbonate. With renal tubular acidosis, the kidneys fail to recover bicarbonate appropriately or fail to excrete acid, leading to a ongoing acid-base problem despite preserved or only mildly impaired kidney function.
In practice, the body often responds by increasing chloride, which is why hyperchloremic acidosis is another typical way to describe this pattern. Students should note that the absence of an elevated anion gap does not mean there is no important acid-base disturbance. It simply points toward a different mechanism.
A structured evaluation should include the history, medication use, kidney function, gastrointestinal losses, and the broader electrolyte pattern. This kind of diagnostic approach is more useful than relying on a calculator result alone.
Stepwise Approach to Acid-Base Imbalances
To analyze any acid-base disturbance, medical students should proceed in a stepwise order rather than jumping immediately to one number. The process starts with the blood gas analysis, then moves to serum electrolytes, then to the anion gap, and finally to compensation and mixed disorders.
A practical stepwise method is:
- Examine the ABG for pH, CO2, and bicarbonate. Determine whether the primary problem is metabolic or respiratory. Calculate the anion gap to sort metabolic acidosis as high gap or normal gap. Evaluate the compensatory response to see whether respiratory response is appropriate. Check the delta gap if the anion gap is elevated to look for additional disorders.
The delta gap helps determine whether the rise in the anion gap is proportional to the fall in bicarbonate. If the change does not fit expectations, a mixed disorder may be present. This matters because a patient can have more than one process at the same time, such as high anion gap metabolic acidosis plus metabolic alkalosis from vomiting.
The compensatory response should always be assessed because the body responds predictably to primary metabolic disturbances. For example, in metabolic acidosis, the respiratory system usually lowers CO2 through hyperventilation. If compensation is absent or excessive, another process may also be occurring.
This framework turns the anion gap calculator into more than a formula tool. It becomes part of a broader systematic evaluation of the patient’s acid-base status.
Typical Errors In Using an Anion Gap Calculator
One common pitfall is failing to anion gap in chronic kidney disease account for albumin. Since hypoalbuminemia lowers the apparent gap, students may fail to identify a clinically important high-gap state unless they apply the corrected anion gap. This matters especially in critically ill patients, where low albumin is common.
Another error is relying on the calculator without checking the actual lab values. The anion gap is only useful if sodium, chloride, and bicarbonate are accurate and consistent. A single transcription error can change the result enough to alter the interpretation.
Students also sometimes forget that a “normal” value does not rule out disease. A patient with severe hypoalbuminemia may have a deceptively normal result even in the presence of significant acid generation. Likewise, a mixed acid-base disorder can hide behind a seemingly straightforward number.
Other common pitfalls include:
- Overlooking the laboratory’s reference interval. Ignoring the role of measurement error in electrolyte testing. Neglecting to relate the result with the patient’s symptoms and diagnosis. Believing all metabolic acidosis is high gap.
The best habit is to use the calculator as an assistant, not a replacement for thinking. Accurate interpretation requires combining the result with the clinical story, blood gas analysis, and the broader metabolic context.
Study Scenarios for Medical Students
Example 1: A patient presents with a serum sodium of 138, serum chloride of 100, and serum bicarbonate of 14. The anion gap is 24, indicating elevation. This pattern strongly suggests high anion gap metabolic acidosis. The next step is to think about causes including lactic acidosis, ketoacidosis, and kidney failure-related acid retention, then correlate with vitals, glucose, creatinine, and lactate.
Example 2: A patient comes in after multiple days of intense bowel losses. Serum sodium is 140, serum chloride is 112, and serum bicarbonate is 18. The anion gap is 10, and that is within the expected range. This is consistent with normal anion gap metabolic acidosis caused by acid-base buffer loss. The higher chloride level supports a hyperchloremic pattern.
Example 3: In a patient with advanced kidney disease, there are sodium 135, chloride 98, and bicarbonate 15. The anion gap is 22, suggesting retained acids and possible uremia. When albumin is low, the albumin-adjusted calculation may reveal an even higher corrected value. That corrected value provides better clinical reading than the raw number alone.
Example 4: In a patient with type 1 diabetes, there is sodium 130, chloride 95, bicarbonate 8, and signs of dehydration. The result points to diabetic ketoacidosis. In this setting, the anion gap calculator helps confirm the presence of a high-gap metabolic process, but treatment decisions depend on the full clinical picture, including glucose, ketones, potassium, and blood gas analysis.
These cases show that the calculator is only a starting point. The true value lies in connecting the number to disease mechanism, diagnosis, and management.
FAQs
What does an anion gap calculator do?
An Anion Gap Calculator is designed to calculate the difference between measured cations and anions from routine labs. It helps evaluate metabolic acidosis, identify unmeasured acids, and guide the diagnostic approach to acid-base problems. It is particularly useful for identifying elevated anion gap metabolic acidosis and deciding whether albumin correction is needed.
How do you calculate the anion gap with lab results?
Apply the formula for the anion gap: sodium less the total of chloride and bicarbonate. In formula form, it is sodium − (chloride + bicarbonate). Input the values into an anion gap calculator to limit arithmetic mistakes, then check the result with the local normal range.
What counts as a normal anion gap range?
The normal range varies with the laboratory method and whether potassium is included. Several laboratories use a non-potassium range around 8 to 12 mEq/L, but students should always use the institution’s stated reference interval. A “normal” value must also be interpreted in light of albumin and the broader clinical picture.
Why should you correct the anion gap for albumin?
You adjust for albumin because it is a major unmeasured anion. In hypoalbuminemia, the measured gap may seem falsely low or normal, which can hide a true acid-base problem. Albumin correction gives a more accurate corrected value and improves clinical interpretation.
What can cause a high anion gap metabolic acidosis?
Major causes include lactic acidosis, ketoacidosis, and uremia. These conditions elevate unmeasured ions and lower bicarbonate, producing high anion gap metabolic acidosis. A careful review of the arterial blood gas, electrolytes, kidney function, glucose, and lactate helps confirm the cause.