What exactly is the Anion Gap?
The anion-gap value is a helpful approach to assess electrolytes and understand the relationship between measured and unmeasured anions in the blood. It is usually derived from a serum chemistry panel and guides clinicians narrow the differential diagnosis for acid-base problems, especially metabolic acidosis.
From a physiology standpoint, the anion gap reflects the gap between the main measured cations and anions in serum. Because routine testing does not directly measure every ion, the calculated value estimates the amount of unmeasured ions present. This makes the anion gap a valuable tool for clinical interpretation and laboratory assessment when evaluating an acid-base disturbance.
Medical students often initially encounter the anion gap as part of a larger serum chemistry or electrolyte panel. It is especially important because a change in the gap can indicate a hidden metabolic derangement even when the pH has not yet been reviewed. In other words, the anion gap is not just a number; it is a clue to the underlying acid-base balance.
How to Calculate the Anion Gap
The anion gap formula is often expressed as:
Anion gap = sodium − (chloride + bicarbonate)In this calculation, sodium is the primary measured cation, while chloride and bicarbonate are the anions that are measured. An anion gap calculator makes easy this calculation from the lab values you enter, helping minimize arithmetic errors during a demanding clinical workflow.
It is simple to use the calculator:
- Type in the serum sodium value. Input the serum chloride value. Input the serum bicarbonate value. The calculator gives the anion gap and often shows whether it is elevated or within the expected reference interval.
For example, if sodium is 140, chloride is 104, and bicarbonate is 24, the anion gap is 12. This is a normal result in many laboratories. The exact interpretation depends on the lab’s reporting method and local reference range, so students should always compare the result with the values provided by the institution.
Understanding the formula matters because the result is only as reliable as the underlying data. If any value is inaccurate due to a measurement error, the calculated anion gap may be misleading. That is why clinicians should always interpret the output in the context of the broader electrolyte disorder and the patient’s clinical picture.
Normal Range and Protein Correction
A normal anion gap is typically set by the laboratory’s normal range, which may differ depending on the analyzer and whether potassium is included in the equation. A common potassium-free delta ratio calculator free reference interval is roughly 8 to 12 mEq/L, but this should not replace the local lab standard.
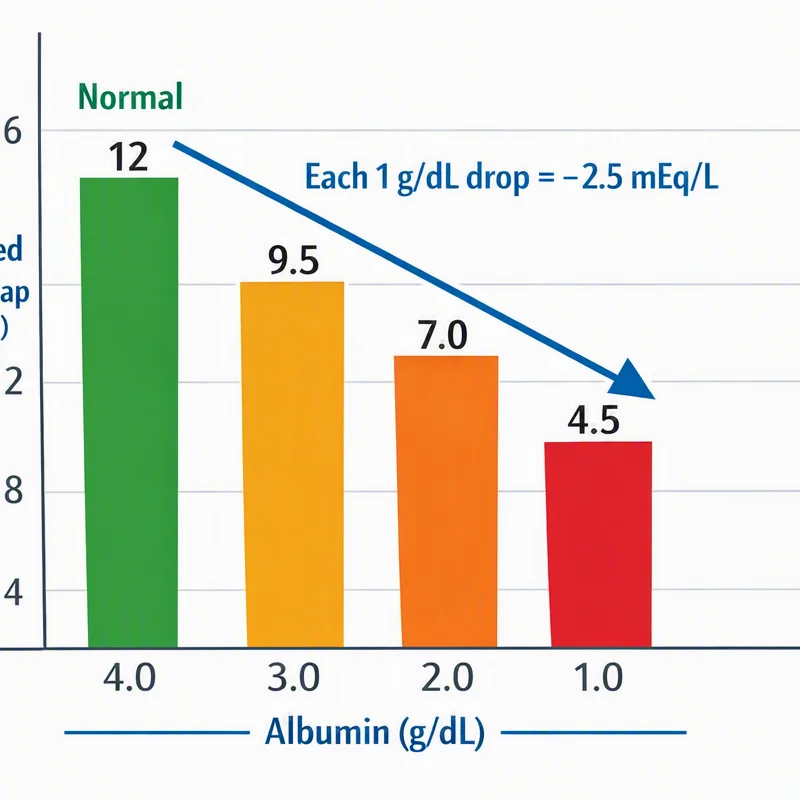
One of the most important adjustments in real practice is the effect of albumin. Because albumin is a major unmeasured anion, hypoalbuminemia can make the anion gap appear falsely low or normal even when an acid load is present. This is why albumin correction is often crucial for accurate interpretation.
A practical way to think about it: when albumin falls, the measured anion gap falls too, because fewer negatively charged proteins are contributing to the total. A corrected value helps identify an elevated gap that might otherwise be missed. In many teaching settings, a commonly used correction is to add approximately 2.5 mEq/L to the anion gap for every 1 g/dL decrease in albumin below 4 g/dL. However, students should follow local anion gap in chronic kidney disease teaching standards and institutional methods.
This is especially important in hospitalized patients, where hypoalbuminemia is common. Without albumin correction, clinicians may miss the severity of metabolic acidosis. A unremarkable result on an anion gap calculator does not always mean the acid-base picture is normal.
Clinical Interpretation of an Elevated Anion Gap
An elevated anion gap points to the existence of additional acids or other unmeasured ions in the serum. This pattern is classically seen in high anion gap metabolic acidosis, a major topic in acid-base medicine. In this setting, the body builds up acids, and bicarbonate is used up as buffering happens.
Common causes include lactic acidosis, ketoacidosis, and uremia. Each has a different pathophysiology, but all can produce a higher-than-expected gap:
- Lactic acidosis: excess lactate from tissue hypoperfusion, sepsis, severe exercise, or impaired lactate clearance. Ketoacidosis: accumulation of ketone bodies in diabetic, alcoholic, or starvation states. Uremia: retention of acids in advanced kidney failure, contributing to the burden of unmeasured anions.
When the gap is elevated, the next step is not merely to label the disorder. Students should ask why the acid is present, how severe the derangement is, and whether there are further abnormalities. The anion gap helps with diagnostic approach, but it is only one piece of the puzzle.
For example, a patient with vomiting, altered mental status, and high glucose may have ketoacidosis. Another patient with hypotension and rising lactate may have lactic acidosis. A third patient with renal failure and elevated creatinine may have uremia. In each case, the same calculator output requires distinct clinical interpretation.
Reasons for a Normal Anion Gap Metabolic Acidosis
Not all metabolic acidosis causes an elevated gap. Normal anion gap metabolic acidosis, also called non-anion gap metabolic acidosis, occurs when bicarbonate is removed or chloride goes up to maintain electroneutrality. In this pattern, the anion gap remains in the usual range even though the patient is acidotic.
The two main causes are diarrhea and renal tubular acidosis. With diarrhea, the gastrointestinal tract loses bicarbonate, producing bicarbonate loss and a decrease in serum bicarbonate. With renal tubular acidosis, the kidneys fail to reabsorb bicarbonate appropriately or fail to excrete acid, leading to a ongoing acid-base problem despite maintained or only mildly impaired kidney function.
In practice, the body often adapts by increasing chloride, which is why hyperchloremic acidosis is another common way to describe this pattern. Students should note that the absence of an elevated anion gap does not mean there is no important acid-base disturbance. It simply points toward a separate mechanism.
A step-by-step evaluation should include the history, medication use, kidney function, gastrointestinal losses, and the broader electrolyte pattern. This kind of diagnostic approach is better than relying on a calculator result alone.
Stepwise Approach to Acid-Base Disorders
To evaluate any acid-base imbalance, medical students should proceed in a structured order rather than going straight to one number. The process starts with the arterial blood gas, then moves to serum electrolytes, then to the anion gap, and finally to compensation and mixed disorders.
A useful stepwise method is:
- Review the blood gas analysis for pH, CO2, and bicarbonate. Figure out whether the primary problem is metabolic or respiratory. Calculate the anion gap to divide metabolic acidosis as high gap or normal gap. Review the compensatory response to see whether respiratory response is appropriate. Consider the delta analysis if the anion gap is elevated to look for additional disorders.
The delta ratio helps identify whether the rise in the anion gap is proportional to the fall in bicarbonate. If the change does not align with expectations, a mixed disorder may be present. This matters because a patient can have more than one process at the same time, such as high anion gap metabolic acidosis plus metabolic alkalosis from vomiting.
The compensatory response should always be assessed because the body responds predictably to primary metabolic disturbances. For example, in metabolic acidosis, the respiratory system usually lowers CO2 through hyperventilation. If compensation is absent or excessive, another process may also be occurring.
This framework turns the anion gap calculator into more than a formula tool. It becomes part of a broader organized evaluation of the patient’s acid-base status.
Frequent Errors In Using an Anion Gap Calculator
A typical pitfall is failing to account for albumin. As hypoalbuminemia decreases the apparent gap, students may miss a clinically important high-gap state unless they apply the corrected anion gap. This matters especially in critically ill patients, where low albumin is common.
One other problem is relying on the calculator without checking the actual lab values. The anion gap is only useful if sodium, chloride, and bicarbonate are reliable and appropriate. A single transcription error can change the result enough to affect the interpretation.
Students also sometimes forget that a “normal” value does not rule out disease. A patient with severe hypoalbuminemia may have a deceptively normal result even in the presence of significant acid generation. Likewise, a mixed acid-base disorder can hide behind a seemingly straightforward number.
Additional pitfalls include:
- Overlooking the laboratory’s reference interval. Overlooking the role of measurement error in electrolyte testing. Failing to connect the result with the patient’s symptoms and diagnosis. Thinking all metabolic acidosis is high gap.
The best habit is to view the calculator as an assistant, not a replacement for thinking. Accurate interpretation requires integrating the result with the clinical story, blood gas analysis, and the broader metabolic context.
Study Examples for Future Clinicians
Case 1: A patient has a serum sodium of 138, serum chloride of 100, and serum bicarbonate of 14. The anion gap is 24, and it is elevated. This pattern is highly suggestive of high-gap metabolic acidosis. Next, consider causes like lactate-related acidosis, ketone-related acidosis, and kidney failure-related acid retention, then correlate with vitals, glucose, creatinine, and lactate.
Example 2: A patient presents after several days of severe loose stools. Serum sodium is 140, serum chloride is 112, and serum bicarbonate is 18. The anion gap is 10, which falls in the normal range. This fits with non-gap metabolic acidosis caused by acid-base buffer loss. The elevated chloride supports a hyperchloremic pattern.
Case 3: A patient with advanced kidney disease has sodium 135, chloride 98, and bicarbonate 15. The anion gap is 22, suggesting retained acids and possible uremia. If albumin is low, the correction for albumin may reveal an even higher corrected value. That corrected value provides better clinical interpretation than the raw number alone.
Clinical case 4: In a patient with type 1 diabetes, there is sodium 130, chloride 95, bicarbonate 8, and signs of dehydration. This pattern indicates ketoacidosis. In this situation, the anion gap calculator helps confirm the presence of a high-gap metabolic process, but treatment decisions depend on the full clinical picture, including glucose, ketones, potassium, and blood gas analysis.
These examples illustrate why the calculator is just the beginning. The true value lies in connecting the number to disease mechanism, diagnosis, and management.
Frequently Asked Questions
What does an anion gap calculator do?
An Anion Gap Calculator is designed to calculate the difference between measured cations and anions from routine labs. It helps evaluate metabolic acidosis, identify unmeasured acids, and guide the workup strategy to acid-base problems. It is particularly useful for identifying elevated anion gap metabolic acidosis and deciding whether albumin correction is needed.
How do you calculate the anion gap with lab results?
Follow the anion gap equation: sodium less the total of chloride and bicarbonate. In formula form, it is sodium − (chloride + bicarbonate). Put the values into an anion gap calculator to limit arithmetic mistakes, then compare the result with the local reference range.
What counts as a normal anion gap range?
The normal range is based on the laboratory method and whether potassium is included. A number of labs use a non-potassium range around 8 to 12 mEq/L, but students should always use the institution’s stated reference interval. A “normal” value must also be considered in light of albumin and the full clinical setting.
Why do you correct the anion gap for albumin?
You modify for albumin because it is a major unmeasured anion. In hypoalbuminemia, the measured gap may seem falsely low or normal, which can hide a true acid-base problem. Albumin correction produces a more accurate corrected value and improves clinical interpretation.
What causes a high anion gap metabolic acidosis?
Major causes include lactic acidosis, ketoacidosis, and uremia. These conditions elevate unmeasured ions and lower bicarbonate, producing high anion gap metabolic acidosis. A detailed review of the arterial blood gas, electrolytes, kidney function, glucose, and lactate helps identify the cause.